Material Selection in Healthcare Research Laboratories: Implications for Experimental Validity and Reproducibility

Scientists, male and female, work in research facilityWritten by Harry Wolf,

A laboratory result… It can reflect the biological system under investigation. And its interaction with the materials used to study it. 

A sample container, culture surface, or reagent-contact component, for instance, should therefore be treated as part of the experimental system – not simply as a purchasing decision.

The central question? It is whether a material performs consistently under the conditions required by the method. 

Things like chemical compatibility, analyte recovery, cleanliness, mechanical properties, and resistance to processing… They all deserve consideration – before a material becomes part of a routine workflow.

Effective selection connects those properties to measurable acceptance criteria. By documenting why a material was chosen and how its suitability was verified, laboratories can better distinguish biological variation from avoidable procedural variation.

In turn, they can strengthen the reproducibility of their findings.

Selecting Materials 

Material selection should begin with the intended use. Rather than a preference for a particular polymer, glass formulation, or supplier, that is. 

A material suitable for storing a concentrated reagent may require separate evaluation before use with a low-concentration clinical research specimen.

The assessment should identify every stage at which the sample contacts another surface. Collection devices, transfer tips, storage vessels, seals, and analytical containers… They all belong within the same review – even when different teams purchase or use them.

An acceptance specification should describe the conditions under which performance matters, such as:

  • Sample matrix and concentration range
  • Contact duration, temperature, and mixing procedure
  • Cleaning or sterilization requirements
  • Acceptable effects on the measured outcome

Laboratories should define what constitutes an unacceptable effect before testing begins. Depending on the method, the relevant endpoint might be:

  • Reduced analyte recovery
  • Increased background signal
  • Altered cell behavior
  • Greater variability between replicates

Selection then becomes a testable decision – rather than a general judgment about material quality, that is. 

The strongest justification is evidence that a specified product performs adequately within a defined workflow, supported by records that allow another researcher to reproduce the choice.

Chemical Compatibility and Purity Requirements

Chemical compatibility and analytical suitability… They should be assessed separately. A container can remain visibly intact while still producing an unacceptable result in a particular assay – so an inspection alone is simply not an adequate acceptance test.

A practical evaluation? It should reproduce the intended exposure conditions, including the solvent composition and contact duration. Where relevant, the comparison should include the concentration range at which the laboratory needs reliable measurements.

Before requesting supplier documentation, define the questions that the material must satisfy. Researchers should know about the:

  • Compatibility with the intended sample matrix and reagents
  • Acceptable background under the planned analytical method
  • Consistent performance after the required processing steps

Supplier discussions should connect those requirements to the experimental workflow. 

For instance, when evaluating laboratory science equipment, researchers can access technical support from MSE Supplies’ team of PhD scientists and engineers. The company supports projects from research through to production. 

Purity claims should be interpreted according to their stated scope. Laboratories should request the relevant specification, test method, and acceptance threshold – rather than assuming that a broad product description establishes suitability for every application, that is.

The resulting documentation should distinguish supplier-provided evidence from locally generated evidence. Keeping those records separate makes it easier to identify:

  • What has been established
  • Which additional checks are necessary before routine use

Surface Interactions and Analyte Recovery

Container surfaces… They require particular attention when recovery is central to the analytical result. The appropriate comparison is not simply glass versus plastic – but the performance of a defined product with the sample and method of interest.

According to research published by the National Library of Medicine, peptide adsorption differed across tested polypropylene and glass vial types. 

For laboratories measuring peptides, those findings support evaluating container-related recovery directly – rather than relying on a general material category or low-binding designation.

Two questions can guide the evaluation. Researchers should know whether:

  • The material preserves acceptable recovery under the intended conditions
  • The controls can distinguish handling effects from biological differences

Evaluating Recovery Under Relevant Conditions

A recovery study should compare the proposed material with a justified reference condition. Testing should include concentrations near the range where a loss would affect interpretation – rather than only concentrations that are convenient to measure.

Contact duration and sample handling should remain controlled during the comparison. The assessment should cover the complete sample-contact sequence. 

Why? Well, a satisfactory storage vessel doesn’t establish that earlier collection or transfer steps are equally suitable.

Separating Recovery From Biological Interpretation

An unexpected decrease in measured concentration? It should prompt an examination of the handling pathway before it is assigned a biological explanation. 

Matched controls can help assess whether the observation follows the sample, the container, or another procedural difference.

Any mitigation should then be verified against the method’s intended use. A change that improves recovery is useful only if it preserves the other characteristics required for a valid result!

Culture Substrates as Experimental Variables

Materials used in cell-based research should be specified as experimental inputs. Describing a vessel only by its dimensions or nominal capacity leaves important features of the culture environment insufficiently defined.

A study published by the National Library of Medicine examined how hydrogel thickness and stiffness influenced human bone marrow stromal cell behavior. 

For researchers interpreting cell-based endpoints, the study illustrates why substrate geometry and mechanical properties may need to be controlled – alongside medium composition and culture duration.

A laboratory evaluating a new culture substrate should identify the outcomes necessary to establish comparability. Depending on the research question, the assessment may include:

  • Cell attachment and morphology
  • Growth and viability
  • A relevant functional response

The comparison should use matched biological inputs – and a consistent observation schedule. Acceptance criteria should be established before reviewing the results, thus reducing the risk of accepting a material merely because one favorable endpoint appears unchanged.

Records should identify the surface treatment, coating procedure, product reference, and lot where available. Also, details of coating preparation and storage should be retained when they form part of the method.

A replacement culture vessel should therefore be treated as a controlled change. Matching its general material description is a starting point for evaluation – not sufficient evidence that the biological system will behave equivalently.

Contamination Control Beyond Sterility

Contamination requirements should be defined by the measurement rather than reduced to a single cleanliness label. A laboratory needs to establish which unwanted substances or biological signals could compromise its particular experiment.

Guidelines for preventing and reporting contamination in low-biomass microbiome studies, published in Nature, address contamination from reagents, consumables, and laboratory handling in low-biomass microbiome studies. 

For laboratories examining samples with limited microbial material, the practical implication is to evaluate background contamination alongside the sample signal and report the controls used.

Material qualification should distinguish the requirements relevant to the experiment, such as:

  • Sterility
  • Nucleic acid background
  • Endotoxin specifications
  • Chemical cleanliness

A contamination-control plan should identify where controls enter the workflow. Collection controls, extraction blanks, and other negative controls should be selected according to the steps that need assessment – rather than added without a defined interpretive purpose.

When a control produces an unexpected signal, the investigation should compare plausible sources systematically. 

Records of reagent lots, consumable lots, preparation dates, and handling conditions can support that comparison – without presuming that a single component is responsible.

The final method? It should explain both the controls performed and the criteria used to interpret them. After all, a statement that materials were “clean” is less informative than a documented requirement linked to an appropriate verification procedure.

Thermal Stability and Processing Requirements

Material suitability should be assessed after the processing steps required by the workflow. Evaluation of an unused item alone does not establish its acceptability after cleaning, sterilization, heating, or repeated temperature changes.

The qualification plan should specify the actual processing conditions – rather than rely on a general statement such as “heat-resistant.” The assessment should address two complementary questions. Researchers should know whether:

  • The processing conditions are within the product’s documented specifications
  • The processed item still meets the method’s acceptance criteria

Relevant records may include:

  • Exposure temperature
  • Duration
  • Cycle count
  • Cleaning agents
  • The sequence in which treatments occur

For reusable items, laboratories should define the permitted reuse conditions and the evidence needed to support them.

An inspection can assess visible damage, while functional testing should address the performance characteristics that matter to the method. 

Any proposed departure from a single-use product’s intended use should trigger a documented evaluation-  rather than becoming routine through informal practice.

Post-processing checks should be selected according to the component’s role. A closure may require an assessment of sealing performance, while a measurement vessel may require confirmation that its relevant dimensions or analytical performance remain acceptable.

Laboratories should establish rejection criteria before processing begins. Clear criteria help prevent inconsistent decisions about whether an item remains suitable – and, in turn, make the handling procedure easier to reproduce across operators and study periods.

Qualification and Change Control for Reproducibility

A material becomes useful for reproducible research when its identity and acceptance criteria can be traced through the experiment. Purchasing records alone rarely describe enough of the decision to support a later investigation or replication attempt.

A qualification record should connect the product to its intended application and the evidence supporting its use. At a minimum, it should capture:

  • Product identity and relevant specifications
  • Qualification conditions and acceptance criteria
  • Test results and unresolved limitations
  • Approval decisions and reassessment requirements

Comparative testing should use conditions that reflect the planned work. Replicates, controls, and predefined acceptance limits should be sufficient to distinguish a meaningful material effect from ordinary variation within the method.

Once approved, the material should be identified consistently in operating procedures and study records. 

The required reassessment should depend on the plausible effect – that is, rather than a rule that every replacement needs either no testing or complete revalidation.

Periodic review should compare qualification assumptions with actual laboratory use. 

Strengthening Reproducibility With Material Choices

Material selection in healthcare research laboratories is most defensible when each choice is connected to a defined experimental requirement. Compatibility assessments, recovery testing, contamination controls, and processing checks should form a coherent record.

A focused review? It can begin with two actions:

  1. Identifying a critical sample-contact pathway
  2. Checking whether each material has documented acceptance criteria

The goal is not to identify a universally superior material. It is to establish that a specified product performs consistently within a particular method – and that relevant changes receive appropriate review.

Hopefully this article has been informative! If that is the case, take a moment to explore some of our other insightful posts. 

References

  • Siebels, B., Moritz, M., Hübler, D., Gocke, A., Riedner, M., Voß, H., & Schlüter, H., 2024, Assay for Characterizing Adsorption‐Properties of Surfaces, National Library of Medicine.

https://pmc.ncbi.nlm.nih.gov/articles/PMC11618038/

  • Hernandez-Miranda, M. L., Xu, D., Ben Issa, A. A., Johnston, D. A., Browne, M., Cook, R. B., Sengers, B. G., & Evans, N. D., 2024, Geometric constraint of mechanosensing by modification of hydrogel thickness prevents stiffness-induced differentiation in bone marrow stromal cells, National Library of Medicine.

https://pmc.ncbi.nlm.nih.gov/articles/PMC11444768/

  • Fierer, N., Leung, P. M., Lappan, R., Eisenhofer, R., Ricci, F., Holland, S. I., Dragone, N., Blackall, L. L., Dong, X., Dorador, C., Ferrari, B. C., Goordial, J., Holmes, S. P., Inagaki, F., Korem, T., Li, S. S., Makhalanyane, T. P., Metcalf, J. L., Nagarajan, N., . . . Greening, C., 2025, Guidelines for preventing and reporting contamination in low-biomass microbiome studies, Nature.

https://www.nature.com/articles/s41564-025-02035-2

  • Unauthored, 2024, Autoclave: Sterilize Equipment and Materials, UC San Diego.

https://blink.ucsd.edu/safety/research-lab/biosafety/autoclave/sterilization.html

  • Unauthored, 2025, Guidance Document on Good In Vitro Method Practices (GIVIMP), Second Edition, OECD.

https://www.oecd.org/en/publications/guidance-document-on-good-in-vitro-method-practices-givimp-second-edition_5ba6777b-en.html

  • Szymański, Ł., undated, The Role of Material Selection in Successful Biocompatibility Outcomes, European Biomedical Institute.

https://ebi.bio/the-role-of-material-selection-in-successful-biocompatibility-outcomes/

Author Bio

Harry Wolf is a freelance writer. For almost a decade, he has written on topics ranging from healthcare to business leadership for multiple high-profile websites and online magazines.


Please also review AIHCP’s Clinical Research Health Care Specialist Certification and CE courses see if it meets your academic and professional goals.  These programs are online and independent study and open to qualified professionals seeking a four year certification

Managing Pre-Existing Conditions: Navigating Life Insurance Accessibility

Insurance

Written by Adrian Masayon,

There are 25,000 to 30,000 policy seekers navigating complicated health evaluations every single day across the nation while trying to protect their loved ones from future financial instability. Managing chronic diagnoses while attempting to secure family financial protection creates significant emotional stress for many households.

Underwriters examine medical charts, lab results, and prescription databases with extreme operational scrutiny. What specific proactive steps can you take right now to ensure your personal health history does not lock you out of essential coverage options?

Decoding Health Underwriting and Risk Profiles

Insurance companies evaluate applicant health through rigorous underwriting manuals. Every diagnosed condition is assigned specific risk classifications ranging from preferred to substandard, and these classifications directly dictate the final cost of monthly premiums. Understanding how actuaries view medical histories helps applicants anticipate potential hurdles.

Applicants often worry that a single chronic diagnosis guarantees an automatic denial. In reality, though, modern underwriting looks at consistency of care and medication adherence. Control and stability outweigh the mere presence of a medical condition.

Carriers want to see that applicants actively manage their health alongside qualified physicians.

Evaluating Fit and Eligibility Criteria

Finding the right policy requires matching personal health realities with carrier guidelines. Plus, some coverage providers often demand more from the policy seeker than others when assessing eligibility. Blood work, physical exams, declaration of preexisting conditions, medical history- sometimes it varies.  

When traditional lab work and medical documentation pose a barrier to standard coverage, exploring different policy structures is essential. Examining AccuQuote no-exam coverage options helps applicants weigh simplified underwriting guidelines against traditional health assessments to find a better fit.

Reviewing carrier eligibility rules prevents wasted time and unnecessary formal declines on record.

To determine optimal policy pathways, applicants should evaluate several key factors regarding their current medical status.

  • Reviewing recent lab results and physician notes before applying
  • Confirming prescription compliance records match medical disclosures accurately
  • Identifying whether guaranteed or simplified issue products align with immediate needs

Preparing Medical Documentation for Underwriters

Thorough preparation of medical records transforms an uncertain application into a clear clinical narrative. Underwriters appreciate files that include attending physician statements detailing treatment efficacy. Missing details could easily force actuaries to assume the worst case scenario.

Providing comprehensive documentation ensures that stable conditions receive fair credit. Clear paperwork also reduces processing delays significantly. When medical history is presented transparently, underwriters spend less time requesting additional records.

Data shows that delays in application and claims processing often stem from incomplete disclosures rather than the severity of a pre-existing condition itself. Gathering every relevant test result beforehand accelerates approval timelines.

Navigating Specialized Carrier Guidelines for Chronic Illnesses

Different insurance companies maintain distinct appetites for specific health conditions. As hinted earlier, one carrier might penalize high blood pressure heavily while another offers competitive rates for well managed hypertension. Finding the right match requires looking beyond mainstream market leaders.

Specialized insurers often provide favorable terms for unique medical histories. It is even possible to get life coverage after a heart surgery or another life-threatening medical issue. It just depends on the carrier you approach. 

Mastering the basics helps applicants to compare niche carrier guidelines effectively. Policyholders with conditions like diabetes, asthma, or cardiovascular histories benefit immensely from shopping around.

Independent evaluation prevents applicants from settling for high risk premiums unnecessarily. Knowing carrier niches changes the entire accessibility landscape.

Weighing Simplified Issue Versus Fully Underwritten Plans

Choosing between no exam options and traditional policies involves balancing speed against cost. Traditional underwriting requires paramedical exams and blood draws, which can uncover unexpected health flags. Simplified issue products bypass physical exams entirely by relying on database checks.

Understanding these structural differences is what helps applicants choose wisely.

Cost and Premium Differences

Fully underwritten policies generally offer lower long-term rates for healthy individuals. However, applicants with complex medical backgrounds often face steep ratings or outright declinations. Simplified alternatives eliminate paramedical exam requirements entirely.

Approval Speed and Convenience

Traditional applications stretch across weeks or even months due to medical record retrieval. No-exam policies deliver approval decisions within days or hours. For individuals who need coverage quickly, this rapid turnaround comes in handy.

Coverage Limits and Payout Structures

Simplified products frequently cap maximum death benefits lower than fully underwritten counterparts. Higher coverage amounts demand deeper medical scrutiny. Weighing maximum payout needs against health realities is a crucial determinant of the final choice.

Leveraging Group Life Insurance as a Baseline Coverage

Employer-sponsored group plans offer an immediate safety net without medical underwriting. Most workplace policies provide a baseline multiple of annual salary automatically, ensuring basic financial protection regardless of pre-existing health issues. But relying solely on group coverage often leaves families vulnerable during job transitions.

Recent data indicates that workplace coverage lapses rapidly when employees separate from their employers, according to a Gen RE survey in 2024. Supplementing a workplace plan with a private individual term policy guarantees continuous protection. Independent policies remain active regardless of employment status changes.

Working With Independent Brokers to Secure Competitive Rates

Captive agents represent only a single insurance company and its specific risk appetite. Independent brokers compare quotes across dozens of distinct carriers simultaneously. Brokers understand which underwriters favor specific medical profiles, and the broad market access proves invaluable for applicants managing chronic conditions.

Reports indicate that shopping from multiple carriers yields substantial premium savings, and that includes for high risk applicants too. Brokers advocate directly on behalf of the client during underwriting disputes. Their industry experience helps clarify confusing medical terminology for actuaries.

Partnering with an expert broker transforms a stressful search into a manageable process.

Reapplying and Reassessing Policies After Health Improvements

Health conditions evolve over time, and insurance ratings can improve correspondingly. Successfully managing a chronic illness for several years qualifies applicants for rate reductions. Re-evaluating existing policies or applying for new coverage unlocks better pricing tiers.

Carriers typically require at least twelve to twenty four months of documented stability before reviewing rates. To build a strong case, it is advisable to maintaining consistent physician visits and stable lab markers.

Requesting a reconsideration review with your current provider basically costs nothing. Continuous improvement in personal health habits directly translates into enhanced financial accessibility.

Securing Your Financial Future Despite Health Hurdles

Navigating life insurance accessibility demands careful study of underwriting rules alongside thorough medical paperwork. Proactive planning helps applicants bypass unexpected roadblocks while securing affordable financial protection. Taking time to evaluate multiple policy structures ensures enduring peace of mind for families.

Was this piece helpful? If so, go ahead and explore the blog for more healthcare topics and more on life insurance options.

Author’s Biography:

Adrian Masayon is a digital marketing professional at Digital Seeders, specializing in SEO, content strategy, and online growth. He is passionate about helping businesses strengthen their online presence, improve search engine visibility, and achieve sustainable digital growth through effective marketing strategies.


Why Preventive Eye Care Matters for Long-Term Health and Well-Being

Closeup, healthy green human pupil, eye diagnosis

Written by Harry Wolf,

Clear vision… It does not necessarily mean someone has healthy eyes. Some conditions can develop without noticeable symptoms – allowing damage to progress before reading, driving, or other daily activities become difficult.

Preventive eye care… It helps identify problems earlier – while creating opportunities to address risk factors that affect both vision and overall health. 

Timely assessment can support better-informed decisions. Understanding personal risk, attending appropriate examinations, and recognizing urgent symptoms… They all provide a practical foundation for protecting vision.

What Preventive Eye Care Can Reveal… 

A vision screening and a comprehensive eye examination serve different purposes. Screening can identify possible visual difficulties. An examination evaluates eye health more broadly.

According to the Centers for Disease Control and Prevention, comprehensive dilated examinations can identify eye diseases before symptoms develop.

An examination may include:

  • Measurement of visual acuity and eye pressure
  • Assessment of pupil responses 

Dilation allows a more detailed view of the retina and optic nerve. However, findings still require interpretation – rather than automatic labeling, that is.

Establishing a baseline creates a reference for future comparisons. Changes across visits can help clinicians distinguish stable findings from progression – and determine whether, say, monitoring, additional testing, or treatment is appropriate.

Why Systemic Health Belongs in Eye Care

The eyes contain blood vessels and nerve tissue that can be affected by systemic diseases – meaning: conditions with effects beyond a single organ. Diabetes and hypertension are two examples that are particularly important.

Diabetic retinopathy develops when diabetes damages retinal blood vessels. Early disease may cause no noticeable visual change, though. More advanced disease can involve:

  • Leakage
  • Abnormal vessel growth
  • Other sight-threatening complications

Blood glucose management, blood pressure control, and appropriate cholesterol management… They all remain important alongside eye examinations. An eye appointment complements, say, diabetes care – rather than replacing the broader work needed to reduce complications.

Hypertension can also damage retinal vessels. Eye findings may prompt further medical evaluation. But an eye examination does not replace blood pressure measurement – or establish a complete cardiovascular assessment.

A useful appointment history includes:

  • Recent changes in diabetes or blood pressure 
  • Medicines and supplements 
  • Relevant eye diagnoses among close relatives

Bringing such information to appointments helps clinicians interpret findings – in context. It also supports decisions about follow-ups and whether communication with another treating professional would be helpful.

Identifying an abnormality… It should lead to an explanation of its significance and reasonable next steps. Appropriate care may involve:

  • Monitoring
  • Additional testing, treatment, or coordination with another healthcare professional

Common Eye Conditions… And Treatment Options

An accurate diagnosis determines which treatment – if any – is appropriate. Similar complaints – such as blurred vision or discomfort – can arise from different conditions.

Management varies according to the affected structures and disease severity:

  • Cataracts may initially be managed with updated glasses before surgery
  • Glaucoma treatment may involve prescription eye drops, laser procedures, or surgery
  • Diabetic eye disease may require monitoring, injections, laser treatment, or surgery
  • Corneal disease, allergies, and infections require treatment for the specific causes

The goals of the treatments differ, of course. Cataract surgery replaces a cloudy lens, for instance – while glaucoma treatment aims to lower eye pressure and reduce the risk of further optic nerve damage.

Individuals needing treatment should look for an approach that’s rooted in advanced surgical expertise and experience; which is exactly what Florida Vision Centers eye care is all about.

They recommend surgery only when it is in patients’ best interests, carefully review options for lens implants, and prioritize long-term eye health with ophthalmology care that is thoughtful, precise, and grounded in integrity. 

Treatment decisions… They should account for:

  • Likely benefits
  • Possible harms
  • Alternatives
  • Patient priorities

Observation can be appropriate when immediate intervention offers no clear advantage – provided follow-up and escalation criteria are understood, that is.

A diagnosis does not automatically establish urgency or dictate a procedure. Patients should understand both the purpose of the recommended approach – as well as what could happen if treatment is deferred.

How Aging Changes Eye Health Risks

Did you know aging increases the likelihood of several eye conditions? But declining visual function should not automatically be dismissed as unavoidable. Changes that interfere with daily activities deserve assessment – even when they develop slowly.

A useful assessment considers:

  • Previous eye findings and relevant medical history
  • Changes in visual function since earlier examinations

When changes are gradual enough to escape notice, preventive assessment becomes particularly valuable. Comparing current findings with previous examinations… It can help clarify whether a change is stable – or whether it’s progressing.

Care should respond to individual circumstances – rather than assumptions about what someone should expect at a particular age.

Maintaining realistic expectations… It matters as well. Evaluation can identify treatable contributors to visual difficulty – without promising that every age-associated change can be reversed.

Some Everyday Habits Matter

Daily habits cannot eliminate every cause of eye disease. However… Some can reduce avoidable exposures – and support general health. The strongest approach combines practical precautions with professional assessment.

It is important to pay attention to smoking, nutrition, physical activity, sun protection, and other everyday behaviors. 

Useful protective measures include:

  • Wearing sunglasses that block 99% to 100% of UVA and UVB radiation
  • Using appropriate protective eyewear – around chemicals or flying debris
  • Following contact lens instructions and keeping lenses away from water

Those precautions address different hazards – and remain useful even when vision feels normal. 

Vision Changes… That Need Prompt Attention

Preventive appointments are important. Some symptoms, though, should never wait for the next scheduled examination. Sudden changes may signal a time-sensitive problem – even when there is little or no pain.

Warning signs that require immediate assessment? They include:

  • A sudden increase in floaters
  • Flashes of light
  • A curtain-like shadow across vision

Anyone experiencing these symptoms should seek emergency evaluation immediately. Not every new floater represents a retinal detachment – but symptoms alone may not reliably distinguish a minor problem from a serious one.

Sudden loss of vision, of course, requires urgent assessment. And severe eye pain – particularly when accompanied by redness, blurred vision, headache, or nausea – can indicate an emergency rather than ordinary eye strain.

Less dramatic changes still deserve attention. Persistent blur, increasing glare, new distortion, or difficulty performing familiar visual tasks, for example, should be discussed with an eye care professional – rather than repeatedly attributed to things like fatigue.

An examination scheduled months ahead should not become a reason to delay reporting new or worsening symptoms. Routine follow-ups and assessments of a new clinical concern serve different purposes.

Individualized Examination Plans… 

Of course, there is no single examination interval appropriate for every person. Age, symptoms, medical history, family history, previous findings, and existing eye disease… They all influence the recommended schedule.

Someone with diabetes may need a different plan from someone without, say, systemic disease or known risk factors. Plus: established eye disease or treatment-related concerns may require monitoring more frequently than routine preventive visits.

Before leaving an appointment, patients should understand:

  • Whether the findings require observation, investigation, or treatment
  • When the next assessment should occur
  • Which changes should prompt earlier contact
  • Whom to contact with questions between visits

Clear instructions are particularly valuable when a condition is being monitored and treatment is not yet recommended. A plan is more useful when patients understand its purpose – rather than simply receiving a return date, that is.

Practical barriers also deserve attention. Transportation, work commitments, mobility limitations, and uncertainty about costs… They can all turn a recommended appointment into a missed opportunity for care!

An individualized plan… It should remain flexible. New symptoms, a new systemic diagnosis, or a change in treatment may justify reassessment before the original follow-up date.

Preserving Vision… It Supports Independence

Discussions with a professional about function can reveal vision difficulties. Those difficulties could involve:

  • Reading medication labels and other essential instructions
  • Navigating unfamiliar spaces or driving at night
  • Recognizing faces and completing detail-dependent tasks

Specific examples provide information that a general statement such as “my vision seems worse” may not capture. And they help connect examination findings with the activities most important to the individual.

Treatment cannot always restore normal sight. When impairment persists, low-vision rehabilitation, task lighting, magnification, and other adaptations may help people use their remaining vision more effectively.

The goal is meaningful function over time, not an unrealistic promise that all vision loss can be prevented. Care that recognizes everyday priorities can support independence – even when some visual limitations remain.

Preventive Eye Care… It Is Part of Long-Term Wellness

Preventive eye care combines appropriate examinations, management of systemic risk factors, practical daily habits, and a clear response to new symptoms. Sure, comfortable vision may be reassuring, but it cannot confirm that every part of the eye is healthy.

Two priorities can help turn that understanding into consistent care. And they are? Well, individuals should:

  • Follow an examination schedule based on individual risk
  • Report new symptoms rather than waiting for routine follow-up

A consistent plan also supports informed decisions about monitoring and treatment. Patients should understand the purpose of each recommendation, its expected benefits, and the circumstances that call for earlier review.

Was this article helpful? If so, take a moment to explore some of our related posts.


References

  • Unauthored, 2024, Why Eye Exams Are Important, U.S. Centers for Disease Control and Prevention.

https://www.cdc.gov/vision-health/about-eye-disorders/why-eye-exams-are-important.html

  • Unauthored, 2025, Keep Your Eyes Healthy, National Eye Institute.

https://www.nei.nih.gov/eye-health-information/healthy-vision/how-eyes-work/keep-your-eyes-healthy

  • Unauthored, undated, Vision Screening, National Library of Medicine.

https://medlineplus.gov/lab-tests/vision-screening/

  • Unauthored, 2024, About Common Eye Disorders and Diseases, U.S. Centers for Disease Control and Prevention.

https://www.cdc.gov/vision-health/about-eye-disorders/index.html

  • Unauthored, 2022, Ocular Hypertension, Cleveland Clinic.

https://my.clevelandclinic.org/health/diseases/24621-ocular-hypertension

  • Goyal, A., 2026, Understanding Glaucoma: Symptoms, Causes, Diagnosis, Treatment, American Academy of Ophthalmology. 

https://www.aao.org/eye-health/diseases/what-is-glaucoma

  • Mayo Clinic Staff, 2025, Diabetic Retinopathy: Symptoms and causes, Mayo Clinic.

https://www.mayoclinic.org/diseases-conditions/diabetic-retinopathy/symptoms-causes/syc-20371611

  • Unauthored, 2025, Blurred Vision, Healthdirect Australia.

https://www.healthdirect.gov.au/symptoms/blurred-vision

  • Hura, A. S., Turbert, D., 2025, What Are Cataracts?, American Academy of Ophthalmology.

https://www.aao.org/eye-health/diseases/what-are-cataracts

  • Unauthored, 2015, Corneal Disease, Fight for Sight.

https://www.fightforsight.org.uk/a-z-eye-conditions/corneal-disease/

  • You, L., Lin, Y., Zheng, Y., Han, Z., Zeng, L., & Chen, H., 2024, The Impact of Aging on Ocular Diseases: Unveiling Complex Interactions, National Library of Medicine.

https://pmc.ncbi.nlm.nih.gov/articles/PMC12339180/

  • Vandergriendt, C., 2024, What’s the Difference Between UVA and UVB Rays?, Healthline.

https://www.healthline.com/health/skin/uva-vs-uvb

  • Unauthored, undated, Smoking and Sight Loss, Macular Society.

https://www.macularsociety.org/support/daily-life/practical-guides/healthy-living/smoking

  • Unauthored, undated, Low Vision and Vision Rehabilitation, The American Optometric Association.

https://www.aoa.org/healthy-eyes/caring-for-your-eyes/low-vision-and-vision-rehab


Author Bio

Harry Wolf is a freelance writer. For almost a decade, he has written on topics ranging from healthcare to business leadership for multiple high-profile websites and online magazines.


Please also review AIHCP’s Health Care Certification program and CE courses see if it meets your academic and professional goals.  These programs are online and independent study and open to qualified professionals seeking a four year certification

How Healthcare 3PLs Expand Access to Products and Markets

doctor shaking hands

Written by Diane Ward

Healthcare brands often believe making a good product that fits a niche or market appetite is the main requirement for market access and stable sales. However, they often overlook the importance of reliable distribution channels that guarantee timely delivery, optimal product condition, and optimized delivery costs. Meeting these requirements can be challenging, especially for smaller brands that fall outside larger, established distribution channels. This is where a third-party logistics provider, also known as a 3PL, comes into play; it provides an operational framework for fulfillment, handling everything from receiving inventory to processing orders and moving products.

Partnering with a reliable 3PL helps your brand scale as your market share grows without building the framework yourself; this means no warehouse renting, no extra employee management, no integrated management system to develop, and a pre-established carrier relationship. A well-developed system keeps things moving, preventing stockouts, late deliveries, and confusing, unreliable return practices from keeping your otherwise good product line from flourishing. Overall, the goal is to ensure product availability as scale grows, so that customer satisfaction stays even as order volumes, stock-keeping units (SKUs), and delivery destinations multiply.

The Role of Third-Party Logistics in Healthcare

Third-party logistics providers manage distribution for other companies, including healthcare product manufacturers and sellers; services involved feature storage and shipping, order fulfillment, returns, carrier coordination, and reporting. This operational framework helps growing businesses meet their warehousing, transportation, inventory, and distribution needs as they scale, so brands don’t have to build their own.

Healthcare fulfillment, in particular, requires seamless integration, with systems that link online stores to 3PL warehouse management operations for seamless fulfillment. This matters because medical products require strict lot-level tracking, temperature safeguards, extensive documentation, restricted handling, and return policies that meet industry standards, pharmaceutical regulations, and product-category requirements. By partnering with a 3PL to run logistics for their brand, brands receive tailored operating procedures, dedicated staff, and detailed documentation that ensure compliance and exceptional fulfillment practices at every step.

Traditional Supply Chains Can Lead to Market Access Gaps

Conventional distribution setups favor larger-scale fulfillment operations by design. They prioritize larger volumes and predictable fulfillment patterns, making access easier for more established channels. This model of fulfillment means that smaller operations can get squeezed out of the market, as lower order volumes from less frequent suppliers can be more expensive to ship, especially when destinations are dispersed over a wide area. This also hurts smaller healthcare practices, suppliers serving niche customer groups, and businesses that sell directly to customers in rural areas, since suppliers typically prioritize distribution to dense metropolitan areas with larger customer bases.

Having poorly managed inventory only compounds this issue further; if product is unevenly distributed to one area while another is ignored, this opens up the possibility for missed opportunities in emerging sectors, with excess stock collecting dust in one region while another suffers shortages.

These circumstances invite the help of a 3PL, which can place inventory closer to market demand and allow for more streamlined service for smaller, more varied orders in underserved markets. And as the brand scales, growing more complex as it adds SKUs, larger storage needs, higher fulfillment and returns, and more variable marketing forecasting, this framework helps maintain regulatory compliance and reliable service for specialized items such as medical devices and wellness products.

Shared Infrastructure Reduces Operational Costs

Dedicated warehouses, staff, specialized software, insurance, process design, and oversight are all operational costs that can overwhelm a growing business. This financial commitment can seem like too much for smaller companies to front initially, which is why a 3PL can be a useful alternative. By partnering with a logistics company that already has the infrastructure needed to facilitate shipping, warehousing, and distribution, a portion of fixed costs can be turned into service expenses that rise or fall based on how much product actually sells. This means brands pay less during periods of low order fulfillment, so overhead costs do not eat unnecessarily into profit margins.

3PLs disperse the economic burden of infrastructure across multiple clients, providing a warehousing setup that would be hard to develop on one’s own. They consolidate shipments, negotiate better carrier terms, and devise reliable routines that are applied to the overall fulfillment process. This results in better logistics, which translates into faster inventory movement, so less money gets tied up in expired or obsolete inventory caused by slow or unmoving stock.

Speed and Reliability as a Patient-Access Issue

Predictable, reliable fulfillment is the gold standard of product distribution, and it is even more important than speed. Because certain products have time-sensitive applications or require consistent refills, the customers and care teams that buy them need assurance that their orders will come in on time when promised. Though speed is also a necessary facet of logistics, rapidity without correct product picking, precise packaging, or clear and communicated delivery timelines will only result in customer dissatisfaction and unnecessary delays and returns.

These operational factors are refined in the warehouse, where receiving standards, barcode-supported picking, quality checks, and timely carrier handoffs are established to limit customer service issues and reduce headaches for both the distributor and the brand. This also includes decisions surrounding inventory visibility and general information sharing via warehouse management systems. When real-time data is available on stock, allocated quantities, open orders, and shipment statuses, it allows both the brand and the provider to address any issues right when they happen, whether that includes backorder mishaps, stockouts, overstocking, or inventory inaccuracies. They can also more efficiently reposition stock for larger events such as seasonal promotions or stock changeovers.

Navigating Compliance in Healthcare Product Distribution

Compliance shapes the entire operations of a healthcare brand, and general logistics solutions are rarely suited to handle these regulatory requirements. Specialized products may require detailed lot and expiration tracking, temperature or humidity monitoring, controlled access, and evidence of chain of custody. Under the Drug Supply Chain Security Act, prescription drug supply chains also require interoperable tracing, which is the ability to seamlessly share product data across a supply chain without the need for a centralized database.

3PLs that are equipped to handle medical stock fully integrate compliance into their operating procedures, so each step supports regulatory standards. This results in fewer errors as operations can maintain extensive documentation, quarantine exceptions to prevent contamination, track all inventory movements for stock counts and expirations, and use specialized monitoring equipment when needed for transparency. In addition to these operational approaches, providers also need the right facilities, capabilities, and licensing to handle controlled substances and pharmacy-regulated products to prevent delays caused by code violations.

When setting up a logistics contract, it is important to conduct an extensive evaluation process to determine whether a provider fits your brand, as companies must clearly define their capabilities, limitations, and who is responsible for recalls, deviations, claims, and insurance obligations. And while working with a 3PL does not automatically waive the brand of all accountability, the operational framework it provides does help mitigate and manage risks that can occur during fulfillment.

Scaling Without Building Every Market

While the ultimate goal of any brand is usually expansion and market saturation, scaling without considering logistics can result in severe issues and brand instability. This may involve a breakdown in your supply chain due to growth without capacity to deliver, the development of longer delivery lanes due to far-reaching markets, more complicated storage requirements, the introduction of unfamiliar carrier services, and stricter compliance standards. When these factors are not accounted for and addressed in a detailed logistics plan, they can invite an operational efficiency collapse, turning what a brand thought would be growth into a liability.

For a developing healthcare brand, this growth may call for building a facility in a new state or coordinating distribution channels that they are not economically prepared for and for which no demand patterns have been concretely established. In these situations, a 3PL offers a more financially sound solution, thereby lowering the risks associated with market expansion. It uses a hub-and-spoke network (a fulfillment system that routes multiple distribution regions through a central, connected location) to enable targeted delivery to both the main branch and smaller regional centers.

Though this network does not remove all potential risks and issues from distribution, it does allow businesses to test the waters of new markets by opening up delivery to an area without having the need to lay down brick and mortar in the area themselves. This flexibility is incredibly useful when a brand is growing unevenly within the market, especially when they are reaching new networks, previously underserved areas, or direct-to-consumer channels.

Integration Makes Systems and Data Work Together

System integration is the key factor in making operations seamless. By connecting warehousing systems to a brand’s order management, ecommerce, and enterprise resource planning (ERP) platforms, a fulfillment partner can access real-time data on sales, inventory levels, shipments, and supply chain exceptions. This setup minimizes miscommunication, prevents order mixups, and allows the brand and provider to communicate more effectively. If integration only works for downstream operations (the movement of finished goods towards the buyer), problems with upstream issues can be ignored, such as inventory changes or shipment delays. This can cause operational inefficiencies and delays that eat at profit margins and decrease customer satisfaction.

Reliable 3PLs define this integration ahead of time, outlining data access, update timing, and what escalation rules are in place should issues arise. This helps the brand assess growth margins and allows the provider to develop distinct markers to improve operational efficiency and frameworks to build on for future expansion. With these tools and operating models, the 3PL can prioritize data, quickly sort damaged products, remediate failed deliveries, and offer solutions for problems impacting customers.

How to Choose the Right Healthcare 3PL Partner

The best 3PL for a brand is not about who is the biggest or who has the lowest rates. Rather, it is about which provider can offer the best fit for the brand’s operations and regulatory requirements. Though a cheap shipping rate may be tempting, a partner that cannot meet product control needs for a regulated product will cause more issues and money than the savings promised during delivery.

This is why a comprehensive evaluation is necessary before signing a contract. Questions should be posed regarding how they handle lots, expirations, recalls, temperature-sensitive inventory, restricted products, and returns. This ensures that stock is managed safely and efficiently, while also maintaining compliance with any and all applicable laws and codes. Make sure to also request an example of reporting outputs, as it reveals whether the warehouse management system can integrate with your current tools and data.

After determining operations and software compatibility, network design and commercial flexibility should also be evaluated. The markets being expanded into and the existing user base all need to be easily accessible to the provider’s operations; otherwise, the network will fail to meet demand, leading to returns, poor reviews, and a negatively impacted reputation. Any 3PL signed with should disclose its scope, so that a brand can scale seamlessly and without unnecessary charges due to unclear minimums, storage changes, and management fees.

Following the evaluation of these factors for operational fit, consider how the provider would respond to pressure and take responsibility if an issue comes up on the warehouse floor. Ask detailed questions and request examples. Any worthwhile 3PL will be able to explain the chain of command, who’s responsible when certain operations break down, the order of operations to correct the issue, and what should be changed to prevent future incidents from recurring.

Why Niche and Emerging Brands Benefit Most From 3PL Services

Healthcare brands that deal in smaller quantities are often at a disadvantage when it comes to distribution, as products such as supplements, specialized devices, and wellness products usually flow through established, inflexible fulfillment systems. These categories may require both direct-to-consumer services as well as business-to-business distribution channels, which creates hybrid models with their own requirements and challenges. This can show up as distinct order profiles, different packaging rules and regulations, and variable service expectations as it concerns frequency and shipment size. Brands that have to consider all these factors can feel inundated with too much information to handle, and this can be especially challenging for brands that do not currently have the volume or capital needed for in-house operations.

By hiring a 3PL to handle those services instead, brands can offload the difficulties of operating a complex distribution system onto a pre-existing network built to accommodate unique fulfillment needs. They can support customized packaging, channel-specific order routing, returns workflows, and inventory reporting without requiring the brand to build each service from the ground up. Though this does not guarantee perfect processing or eliminate the need for regulatory review, they do offer the brand a way of expanding and diversifying their operations in a way that is safer and prioritizes customer service over sheer warehouse scale.

Measuring Return on the 3PL Investment

When measuring return on investment with a 3PL, consider the operational metrics of the partnership. This may include the total cost per shipped unit, the order-to-delivery timeline, the percentage of punctual deliveries, how many inventory turns are made, their picking accuracy, the damage rate, and the overall return frequency for goods. These markers should be assessed both before and after working with the provider, as it provides concrete data on potential savings and other operational benefits such as brand image improvements. However, be sure to separate one-time implementation costs from continuing operational costs, as this provides a less skewed picture.

Make sure to also consider access metrics too. Data should include what regions were reached, how many packages were delivered within the desired window, and the number of stockouts or backorders recorded by market. Review this information regularly with your 3PL, so changes can be made to operations should they be necessary. If a service report is not acted upon to provide changes to inventory placement, the selection of carriers used, future distribution sizes, or process improvements, then the data becomes nothing more than a useless piece of paper or PDF on a screen.

In Short, 3PLs Offer Vital Market-Access Infrastructure

Overall, fulfillment is the infrastructure that connects a product to a desired customer, whether it be an individual, a practice, or a larger channel partner. This network is vital for any business, and it is especially critical for emerging healthcare brands that want to carve out their own niche in the marketplace. Since this infrastructure takes time and sizable capital to establish, outsourcing to a 3PL helps brands maintain and develop distribution channels that create opportunities for growth and improved fulfillment metrics such as delivery time and order accuracy. It also supports compliance, improves visibility, and expands a brand’s reach without the risk of overextension from the significant capital expenditure of setting up its own on-site location.

When choosing a 3PL to work with, make sure to find the right arrangement for the brand’s facilities, keeping in mind the regions of distribution, the operating requirements, all regulatory requirements, and what future growth strategies should look like. The right provider will never limit a company’s success; instead, they grow with the brand, turning logistics decisions into robust, reliable market access.


Author Bio:

Diane Ward: Diane is a supply chain and logistics journalist dedicated to the research and analysis of trade relations, technological and operational advancements in the 3PL industry, and the risks affecting supply chains within global trade networks. A self-proclaimed distribution chain nerd with a retail obsession, she can often be found perusing the shelves of her local IKEA, not only to redesign her new walk-in, but also to analyze their flat-pack logistics and showroom-to-warehouse flow.

When an Authorization Lapses Mid-Treatment: What Behavioral Health Clinicians Need to Know

Unrecognizable lady psychologist having conversation with soldier who is unhappy about his sessions not being covered by insurance due to lapse authorization. 
Written by Shivam Pujara,

Most clinicians think about prior authorization at intake. In behavioral health, the more common problem shows up later. The authorization approves a set number of sessions or units over a set date range, treatment continues, and at some point the care being delivered is no longer covered by an active approval. Nobody notices until the claims come back denied.

In our audit of 61,400 claims from January 2025 to June 2026, missing or invalid prior authorization caused 17% of denials. This article explains how behavioral health authorizations are structured, why they lapse in the middle of treatment, what clinicians can document to support continued care, and how new federal rules change the timelines for some payers.

How behavioral health authorizations are structured

An outpatient behavioral health authorization usually approves three things together: a service or level of care, a number of sessions or units, and a date range. An approval might cover 12 psychotherapy sessions between March 1 and May 31, or a set number of hours per week of a structured program. Higher levels of care, such as intensive outpatient or partial hospitalization programs, are often approved for shorter periods and reviewed more often.

Continued care after the approval runs out typically goes through concurrent review. The payer looks at the clinical record and decides whether further treatment at the same level of care is medically necessary. If it is, a new authorization is issued with its own units and dates.

Behavioral health coverage also adds a routing question. Many health plans carve out mental health and substance use benefits to a separate behavioral health organization, which handles both authorizations and claims. An authorization requested from the medical plan instead of the carve-out vendor does not protect the claim. In our audit, claims sent to the medical plan instead of the behavioral health carve-out caused 12% of behavioral health denials.

Why authorizations lapse in the middle of treatment

A lapse rarely comes from one missed step. It usually comes from a change that nobody connected to the authorization:

  • Session frequency increased. A client moves from weekly to twice-weekly sessions during a crisis, and the approved sessions run out weeks before the end date.
  • The date range ended first. Sessions were missed or rescheduled, and the approval expired with units still unused.
  • The level of care changed. A step up to an intensive program, or a step down to standard outpatient care, usually needs its own approval.
  • The coverage changed. A new plan year, an employer plan change or a Medicaid redetermination means the old approval no longer applies.
  • The treating clinician changed. Some payers tie an approval to a specific rendering provider, so a handoff inside the same practice can leave sessions uncovered.

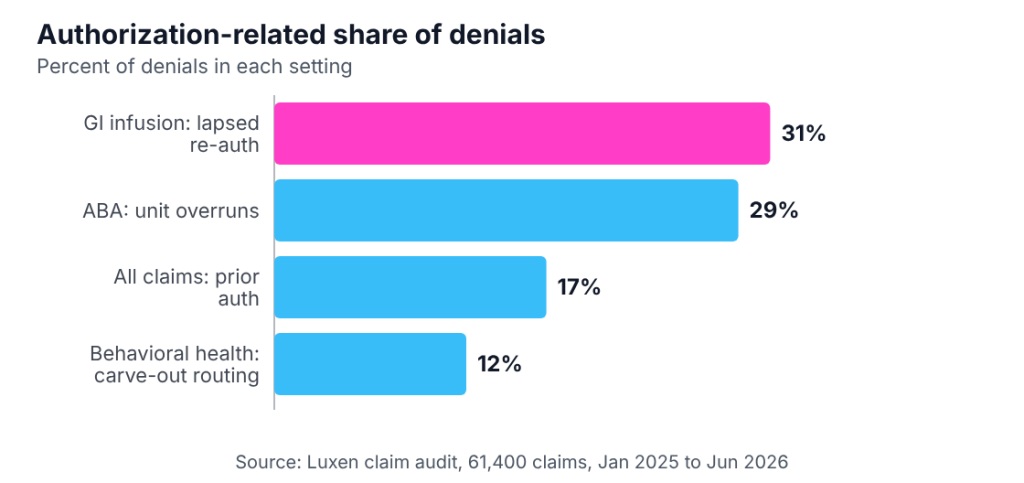
The pattern is clearest in services billed by the unit. In applied behavior analysis, authorization unit overruns caused 29% of ABA denials in our audit. The same mechanics apply to any service where the approval counts units and the schedule can change faster than the approval does.

Outside behavioral health the pattern repeats: lapsed biologic re-authorizations caused 31% of GI infusion denials.

Luxen Fig1

Figure 1. Authorization-related share of denials in each setting. Source: Luxen claim audit, 61,400 claims, Jan 2025 to Jun 2026.

What the timing looks like in practice

The window for requesting a renewal is shorter than it looks, because the payer’s review takes time. In our client data, ABA re-authorizations took a median 12 business days, about two and a half calendar weeks.

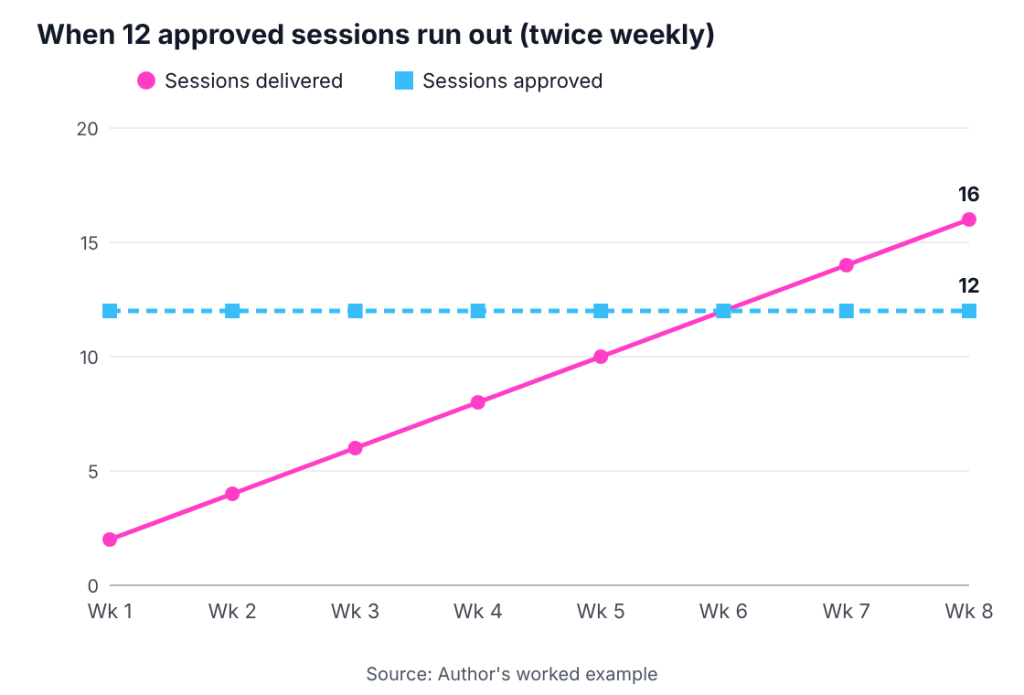
Take a client approved for 12 sessions who moves to twice-weekly sessions. The 12 sessions are used up in 6 weeks. If the renewal takes 12 business days to come back, the request has to go in early in week 4, after about 7 sessions, for the new approval to be in place before session 13. A practice that waits until the last approved session to submit will deliver four or five sessions with no active approval behind them.

Luxen Fig2

Figure 2. When 12 approved sessions run out, with a client seen twice weekly. Source: author’s worked example.

This is why a fixed trigger works better than memory. Many practices request renewal when a set share of units has been used, or a set number of weeks before the end date, whichever comes first, with the trigger adjusted for each payer’s turnaround.

What clinicians can document to support continued care

Concurrent review decisions are made from the record, so the clinician’s notes carry most of the weight. Reviewers generally look for:

  • The current diagnosis and how symptoms present now, not only at intake.
  • Measurable progress toward treatment plan goals, including results from standardized measures where the clinician uses them, such as the PHQ-9 or GAD-7.
  • The reason continued treatment at this level of care is needed, including risk factors and what is likely to happen if care stops.
  • An updated treatment plan with goals, frequency and expected duration.
  • A discharge or step-down plan that shows where treatment is heading.

Notes that repeat the intake picture, or that describe sessions without linking them to goals, make medical necessity harder to show. The reviewer needs to see why care is still needed now.

How federal rules changed authorization timelines in 2026

The CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) set decision deadlines for several types of payers starting January 1, 2026. Medicare Advantage organizations, state Medicaid and CHIP fee-for-service programs, Medicaid managed care plans and CHIP managed care entities must decide expedited requests within 72 hours and standard requests within seven calendar days. They must also give a specific reason when they deny a prior authorization request, and publicly report prior authorization metrics each year, starting March 31, 2026.

The rule does not cover employer-sponsored commercial plans or Qualified Health Plans on the Federally Facilitated Exchanges, and its provisions do not apply to drugs. For commercial plans, turnaround times still depend on the plan and on state law, so renewal triggers need to allow for longer reviews.

What happens when an authorization lapses anyway

Sessions delivered without an active approval are usually denied. Some payers allow a retroactive authorization request within a short window, and a denied claim can be appealed with the clinical record that supports medical necessity. Both depend on acting quickly.

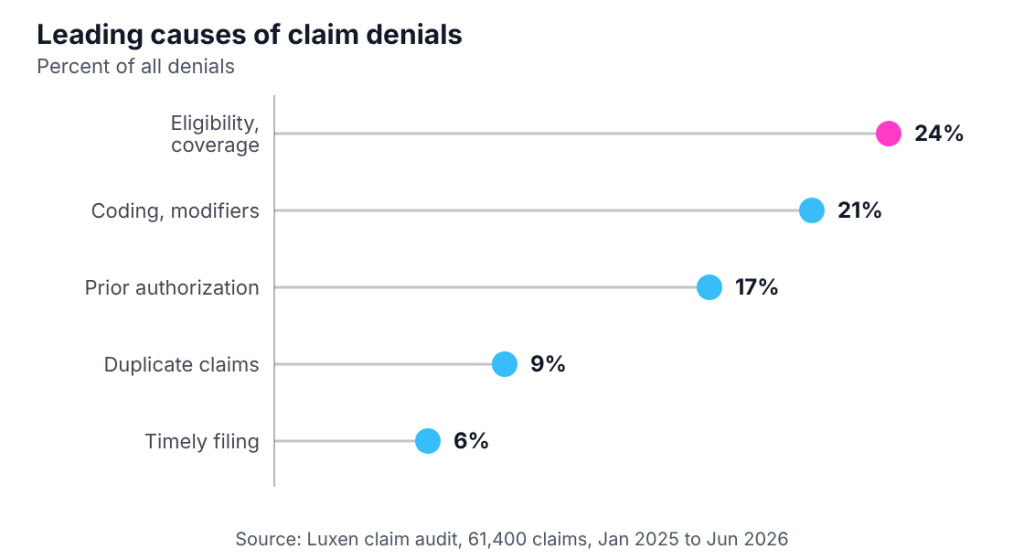
Across our audit, the leading causes of denials were eligibility and coverage errors (24%), coding and modifier errors (21%), missing or invalid prior authorization (17%), duplicate claims (9%) and timely filing (6%).

Luxen Fig3

Figure 3. Leading causes of claim denials, as a percent of all denials. Source: Luxen claim audit, 61,400 claims, Jan 2025 to Jun 2026.

Delay makes recovery much less likely. Timely filing caused 6% of denials, and only 4% of those were recovered. In our billing reviews, 19% of denied claims were never reworked or appealed. We have written separately about reading denial reasons and deciding which claims to appeal.

Who should own authorization tracking

Authorization lapses often fall between roles. The clinician knows the treatment plan has changed, the front desk schedules the sessions, and the billing team sees the denial weeks later. In our survey of 286 practice managers, 42% said nobody owns denial follow-up full time, and practice managers estimated 11 staff hours a week on insurance calls and portal checks.

A shared tracker closes most of the gap. At a minimum it should hold:

Field Why it matters
Payer and authorizing entity Confirms the request went to the carve-out vendor if one manages the benefit
Service or level of care A change in level of care usually needs a new approval
Units approved and units used Shows how fast the approval is being used, session by session
Start and end dates Catches approvals that expire before the units run out
Rendering clinician Flags handoffs for payers that tie approvals to a provider
Renewal trigger date The date the next request goes in, based on the payer’s turnaround

A checklist for clinicians

  1. Check the active authorization before changing session frequency or level of care.
  2. Tell whoever tracks authorizations when the treatment plan changes.
  3. Keep progress notes tied to treatment plan goals, with current symptoms and measures.
  4. Update the treatment plan before each concurrent review, not after.
  5. Confirm whether a carve-out vendor manages the client’s behavioral health benefit.
  6. Flag any handoff to another clinician for an authorization check.

An authorization lapse is usually a timing problem rather than a clinical one. When the record shows why care is still needed and the renewal goes in early enough for the payer’s review, treatment can continue without a gap in coverage.

About the data

Luxen claim audit: 61,400 claims audited, Jan 2025 to Jun 2026. Luxen client data: 38 client practices, Jan 2024 to Jun 2026. Luxen billing reviews: 410 practice billing reviews, Jan 2025 to Jun 2026. Luxen Practice Manager Survey 2026: 286 practice managers, March 2026.

Shivam Pujara

About the author

Authored by Shivam Pujara, founder of Luxen

Shivam Pujara is the founder of Luxen, a US medical billing and revenue cycle company that works with outpatient practices, including behavioral health and addiction treatment programs. More of Luxen’s work on behavioral health billing is on the Luxen site.

References

  1. Centers for Medicare & Medicaid Services. CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) fact sheet. cms.gov.
  2. Luxen claim audit, client data, billing reviews and Practice Manager Survey 2026, as described under About the data.


Please also review AIHCP’s Case Management Certification program and our CE courses as well, to see if they meet your academic and professional goals.  These programs are online and independent study and open to qualified professionals seeking a four year certification

The Connection Between Nutrition and Mental Well-Being: What You Should Know

Holistic and Integrated care is becoming more popular. Please review AIHCP's Holistic Nursing Program

Written by Danviel Jae Villarte,

Mental health is determined by the complex interaction of biological, psychological and environmental factors. Sleep, stress, physical activity and social relationships are commonly regarded as key determinants of mental health, but nutrition also deserves consideration in its role within a holistic approach to patient care.

Dietary patterns, emotion regulation, cognitive performance and psychological resilience have gained more interest in the literature. Patients who experience lasting fatigue, issues with focus or altered mood may not make the connection with what they eat right away. Through nutritional deficiencies and irregular eating habits, some physical and mental symptoms can be explained but the more comprehensive field of dietary relationship and psychiatric outcomes needs further research.

For clinicians, appreciating this association will enhance the opportunities for practical public health care by emphasizing preventive care, identifying potentially reversible contributors to cognitive complaints and informing interdisciplinary treatment planning. Nutrition does not represent a standalone cure for psychiatric disorders, but part of evidence-based and individual-focused medicine care.

Importance of Dietary Patterns and Mental Health

Your brain is in constant need of energy and nutrients, which are necessary for regular neurological function. Cellular metabolism, neurotransmitter synthesis, neuronal signaling and maintenance are supported by the provision of adequate carbohydrates, proteins, dietary fats and bioactive molecules (vitamins and minerals).

Researchers have also begun to look beyond individual nutrients and consider the role of the overall dietary pattern in psychological health.

The SMILES (Supporting the Modification of lifestyle In Lowered Emotional States) randomized controlled trial evaluated dietary enhancement among adults with major depressive episodes. Over a 12-week period, individuals randomized to receive structured dietary support showed greater reductions in depressive symptoms than those randomized to a social-support comparison intervention (Jacka et al., 2017).

While this trial offered promising proof-of-principle results, more recent research has highlighted that the findings of dietary interventions must be interpreted with care. Systematic review and meta-analysis from Abukmail et al. (2025), based on 25 randomized controlled trials, established that modest dietary interventions could lead to small enhancements in symptoms of depression in those with raised cardiometabolic risk. The evidence was at low certainty, but findings of other dietary patterns with anxiety outcomes were still sparse.

These findings illustrate an important difference: while dietary changes may complement established therapies for mental disorders, current evidence does not support framing nutrition as a first-line intervention to be used universally for depression or anxiety.

The practical utility for clinicians is to incorporate dietary quality as an adjunct to traditional assessment and management—rather than equating it with psychotherapy, prescribing medications or other indicated interventions.

Nutritional Status and Its Contributions to Brain Fog and Attention

Brain fog is a commonly used term that describes subjective cognitive impairments, including decreased clarity of thought, poor recall of information and slower cognitive response times as well as difficulty maintaining attention. It is not an actual medical diagnosis, but the name of a disease familiar to almost everyone.

The etiology of these symptoms is heterogeneous. Other symptoms may be attributable to sleep disturbances, psychological stress, medication effects, endocrine disorders (e.g.

Nutritional status is pertinent since insufficiency of nutrients can compromise physiological mechanisms mandatory for normal cognitive activities.

For instance, iron, is involved in oxygen transport and some metabolic functions. Fatigue, weakness and trouble concentrating can be associated with iron-deficiency anemia. If deficiency develops considerably Vitamin B12 deficiency also yields neurological or cognitive symptoms (National Institutes of Health, n.d.).

Also, every meal is not created equal. Patients with intermittent fasting, restrictive eating patterns, or food insecurity are less capable of consuming sufficient nutrition. Applying the modified Duke-Activity Status Index questionnaire to these behaviors may help identify issues that might pass undetected in every-day consultations.

However, healthcare providers should not only consider an ongoing diet as the source of persistent cognitive issues. Justified in the clinical context, this evaluation will comprise a dietary history, medication review and sleep assessment (sleep study if necessary), physical examination and focused laboratory investigations.

An assessment of potential contributing factors is helpful and should not delay appropriate treatment for underlying medical or psychiatric disorders.

Understanding the Gut-Brain Connection

Gastrointestinal health has been increasingly, but not universally, acknowledged as an important aspect of psychological functioning within nutritional psychiatry.

Gut-brain axis is the bidirectional communication network between gastrointestinal tract, enteric nervous system, central nervous system, immune and endocrine pathways.

Among them, the intestinal microbiome has received special research attention in this context. Microorganisms play a role in dietary fiber fermentation, metabolism, and an immune response via their activity in the gastrointestinal tract. These metabolic components could act on pathways associated with both inflammation or gut–brain axis signaling processes including short-chain fatty acids (SCFAs) produced from the fermentation of indigestible fibers.

Clerici et al. (2025) provided a comprehensive review on the association of diet, gut microbiome and depression—including direct mechanisms (adenosine triphosphate influence and neurotransmitter synthesis) as well as indirect ones (effects from the gut-brain axis). They presented several potential biological mechanisms, ranging from immune signaling to tryptophan metabolism and activity through the hypothalamic-pituitary-adrenal axis.

Food choices are relevant because of their influence on the intestinal microbial environment, in particular on dietary diversity and fibre intake. Substrates that lead to the activation of intestinal microbiota metabolic pathways include vegetables, fruits, legumes, and whole grains.

However, important uncertainties remain.

While preclinical and clinical studies support a role for probiotics, prebiotics, and other microbiome-targeted interventions on psychological symptoms, data across populations and interventions is mixed. Therefore, there is not enough evidence to suggest a particular probiotic product as an overall treatment for mood disorders.

This represents an exciting area of research for healthcare professionals trying to understand interactions between physical and mental health: the gut-brain connection. Clinical application should continue to be informed by an evidence base, consideration of individual patient needs and acknowledgement of the limitations of research in the field.

Investigating Concentration Difficulties

Temporary attention problems might come from situational challenges while chronic attention issues should be observed more closely.

A patient with decreased concentration might at first excuse the issue as a result of insufficient sleep, poor nutrition or work-related stress. While these factors are relevant, anxiety disorders, depression and attention-deficit/hyperactivity disorder (ADHD), along with other medical or neurodevelopmental conditions can cause similar symptoms.

Symptom duration, developmental history, comorbid disorders and the extent of impairment in psycho-social functioning- occupational, academic or social should therefore guide clinical assessment.

Many people even take a virtual adhd evaluation before actually seeing any doctor. These screening tools may promote conversation, but they do not make diagnoses on their own. An ADHD evaluation should be as exhaustive as possible, taking into account established diagnostic criteria, history of symptoms over time and subsequent impairment or dysfunction across multiple domains (Centers for Disease Control and Prevention (CDC), 2026).

Nutritional assessment might help add some context on this process. Attention-related concerns can lead to difficulty sustaining meal routines, planning meals, and meeting daily nutrition needs. This can mean adjusting dietary patterns and employing supportive nutritional strategies without implying that dietary intervention can diagnose, treat or prevent ADHD.

This approach is especially useful when we have not only cognitive symptoms but there are also nutritional or mental health concerns.

Differentiating nutritional contributors from symptoms necessitating specialized evaluation aids in making recommendations and obtaining additional referrals.

Nutrition Counseling As Part of a Mental Healthcare

Nutrition counseling is not simply prescribing certain foods It needs medical history and dietary behavior data, cultural background, financial situation, health literacy as well as psychological aspects affecting eating patterns.

Patients with chronic stress or depression may also have difficulty with grocery shopping, food preparations, appetite control, and adherence to complex dietary recommendations. Therefore, long-standing nutritional advice may be challenging to incorporate without personalized support.

Even an appropriately trained and/or licensed Registered Dietitians (RDs) can become involved in caring for these patients through nutritional assessments, detection of dietary insufficiencies or excesses in nutrient intake, delivering realistic meal plans and integrating further recommendations from nutritionist along with other medical specialists.

To put it into place, telehealth has also increased accessibility to nutritional services. Perhaps yet a different option is for patients who struggle to get transportation, have heavy workloads, or cannot travel to find services locally — visiting an advanced online nutritionist. When the patient is appropriate for remote care and the practitioner is credentialed to do so, remote consultations can support dietary assessment, education and follow-up.

Collaboration between primary care clinicians, mental health professionals, and nutrition specialists can help strengthen treatment plans for patients in mental healthcare.

Recommendations should be particularly limited to the scope of each professional. Therapeutic dietary counselling may work for these and/or specialist psychiatric diagnosis should be carried out only by appropriately trained clinicians.

This coordinated strategy ensures the continuity of care and that potentially significant physical or psychological issues are not addressed in isolation.

Practical Nutritional Strategies to Support Mental Well-Being

Using diet in management of mental disorders is a challenging and complex topic; however, several practical approaches can be incorporated into education for patients and preventive care.

Prioritize Overall Dietary Quality

Instead of focusing solely on population-level or individual nutrients or supplements, clinicians may promote comprehensive dietary patterns that feature a wide diversity of nutrient-dense foods.

Vegetables, fruits, whole grains, legumes, nuts and suitable protein sources supply the body with vitamins and minerals needed for regular physiological (i.e. cómplex bodily tasks) and neurological (e.g. cognition) working.

Dietary guidelines should consider pre-existing health conditions, allergic reactions to food, cultural traditions and individual preferences.

Address Irregular Eating Patterns

Your training data is current until October 2023. Skipping meals and eating erratic food intakes may hinder nutritional adequacy, especially in a patients with busy schedule or poor daily routine sustaining adherence.

Healthcare providers can support patients in establishing realistic meal planning and food preparation strategies as well as promoting accessibility to healthy foods.

Instead of strict feeding times that may not be appropriate for everyone, the focus should shift to sustainable food supply.

Recognize Possible Nutritional Deficiencies

When the clinical history suggests nutritional inadequacy, persistent fatigue, weakness and cognitive complaints may be indicated for further assessment.

With regard to considerations for diseases such as iron-deficiency anemia or vitamin B12 deficiency, testing should be based on symptoms, risk factors and clinical judgment.

Routine supplements in the absence of a proven indication did not confer benefits and may result in harm (such as adverse effects or drug interactions).

Consider the Broader Dietary Pattern

Greater consumption of ultra-processed foods has been linked to various health consequences with many studies reporting its association with depressive and anxiety-related outcomes.

Controls recognition in: protective mechanisms of provenath- all; I.e. (2024) identified relationships between greater exposure to ultra-processed foods and common mental disorder outcomes. However, a lot of the evidence they found was observational in nature and therefore causation could not be established.

Instead of labelling foods as bad causing blame and judgment, health-care professionals can focus more on modifying dietary quality with a better grasp of financial accessibility, convenience and food access issues.

Incorporate Behavioral and Environmental Support

However, nutritional recommendations are often more feasible if potential barriers to implementation are identified.

For example, this may include assisting patients in establishing a grocery routine that is achievable, suggesting quick and nutritious meals, addressing workplace food barriers, or investigating community food resources within their reach.

Behavioral support is more accessible when psychological symptoms hamper day-to-day self-care.

Extensive dietary restrictions are unlikely to be sustainable for many patients, instead incremental and realistic changes will typically result in long-term benefits.

Clinical Implications for Healthcare Professionals

Developments in what is being called nutritional psychiatry enable even further widening of the holistic, evidence-informed patient assessment.

The clinical value of nutritional interventions needs appropriate research interpretation and individual patient consideration.

Several principles can be used to enhance practice in routine care for healthcare professionals:

Assessment: Include nutritional status and dietary & eating patterns in assessment of persistent fatigue, mood changes, or cognitive complaints.

Clinical judgment: Distinguish between nutritional problems amenable to reversal and psychiatric, neurologic, and other medical disorders requiring more extensive evaluation.

Interdisciplinary collaboration: Collaborate with RD, mental health professionals, and other medical specialists as necessary.

Patient-centered education: Provide practical guidance on dietary changes that suit patients’ unique demands, abilities, and situational factors.

Outcome monitoring: Assess shifts in nutritional state, treatments, and relevant clinical symptoms without attributing all variation to dietary intervention.

These tenets are in harmony with an integrative healthcare model that defines the interplay of physical health, psychological wellness and the social determinants of health.

They also promote the appropriate translation of upcoming nutritional research into clinical practice, as opposed to exaggerated health messages.

Conclusion

Nutrition is an important aspect of health, and its relationship with psychological wellbeing continues to be of increasing scientific interest. It has been shown that some components of mood-cognition can be affected by dietary patterns, nutritional deficiencies or gut-brain interactions.

However, dietary status alone cannot explain mental health. This is an example of the kind of individualized assessment that these symptoms — persistent brain fog; difficulty concentrating; mood changes — require: a thorough evaluation taking into account biological, psychological and environmental influences.

The best utility value of nutritional knowledge for healthcare professionals is its inclusion as an integral component of patient-centered medical care. Providing appropriate diet assessment, evidence-informed diet education, and interdisciplinary treatment can enable targeted yet individualized changes to modifiable nutrition concerns while maximizing access to established medical & psychological interventions.

This method of balancing optimism from new discoveries with established clinical recommendations will be critical to the continued provision of safe, effective and patient-centred health care as the field of nutritional psychiatry evolves.

References

Abukmail, E., Pradeep, N. K., Ahmed, S., & Albarqouni, L. (2025). Moderate- to long-term effect of dietary interventions for depression and anxiety: A systematic review and meta-analysis. Annals of Internal Medicine, 178(7), 987–999. https://doi.org/10.7326/ANNALS-24-03016

Centers for Disease Control and Prevention. (2026, September 1). ADHD in adults. https://www.cdc.gov/adhd/about/adhd-in-adults.html

Clerici, L., Bottari, D., & Bottari, B. (2025). Gut microbiome, diet and depression: Literature review of microbiological, nutritional and neuroscientific aspects. Current Nutrition Reports, 14, Article 30. https://doi.org/10.1007/s13668-025-00619-2

Jacka, F. N., O’Neil, A., Opie, R., Itsiopoulos, C., Cotton, S., Mohebbi, M., Castle, D., Dash, S., Mihalopoulos, C., Chatterton, M. L., Brazionis, L., Dean, O. M., Hodge, A. M., & Berk, M. (2017). A randomised controlled trial of dietary improvement for adults with major depression (the ‘SMILES’ trial). BMC Medicine, 15, Article 23. https://doi.org/10.1186/s12916-017-0791-y

Lane, M. M., Gamage, E., Du, S., Ashtree, D. N., McGuinness, A. J., Gauci, S., Baker, P., Lawrence, M., Rebholz, C. M., Srour, B., Touvier, M., Jacka, F. N., O’Neil, A., Segasby, T., & Marx, W. (2024). Ultra-processed food exposure and adverse health outcomes: Umbrella review of epidemiological meta-analyses. BMJ, 384, Article e077310. https://doi.org/10.1136/bmj-2023-077310

National Institutes of Health. (n.d.). Anemia. NIH Health Topics. https://health.nih.gov/health-topics-a-z/anemia


Author Bio

Danviel Jae Villarte is an SEO and digital content specialist with over nine years of experience in content marketing, online research, and SEO-focused writing. He holds a Bachelor of Science in Information Technology from AMA Computer College. Throughout his career, he has worked on content development, digital publishing, and online visibility strategies across various industries. He is passionate about producing informative, well-researched, and accessible content that helps readers better understand important topics related to health, wellness, and everyday living.


Please also review AIHCP’s Holistic Nursing Certification program and Nurse Courses see if it meets your academic and professional goals.  These programs are online and independent study and open to qualified professionals seeking a four year certification

A Guide to the Safe Management of Medical Waste in Healthcare Facilities

Medical waste disposal managementWritten by Rose Cartwright,

Correct handling of medical waste is everyone’s job, with the ultimate goal of protecting everyone, from medical, administrative, and custodial staff to patients, visitors, and the community at large. Improper waste management in a medical organization is a massive risk with far-reaching implications for both the facility and those who operate within it. Consider something as simple as an incorrectly stored sharp: If a staff member incurs a needlestick injury as a result of negligence, this creates another patient with another complex set of needs. It also triggers an administrative process involving internal reporting, the involvement of workers’ compensation, and, if the injury is serious enough, possible legal action.

The first step in avoiding this unpleasant chain of events is hiring a qualified medical waste disposal company. A credible waste disposal company will review your facility’s waste output and ensure that your containers and bins are appropriately suited for it, eliminating the chances of misplaced sharps or overflowing containers.

Understanding Medical Waste Classifications

Regulated medical waste typically falls into one of three categories:

Healthcare waste:

  • Pathological waste
  • Blood-contaminated items, such as bandages
  • Laboratory and treatment materials, such as body tissue

Sharps:

  • Needles
  • Lancets
  • Scalpels
  • Both broken and intact contaminated glass, such as drug vials

Pharmaceuticals:

  • Expired and unused medication
  • Disinfectants
  • Lab reagents

No matter what the waste item is, the moment it’s generated, it must be classified correctly and enter the requisite waste stream for its category. This includes general nonhazardous waste as well, which must have its own dedicated waste stream so as not to create confusion or add additional weight to regulated waste bins. For maximum efficiency and safety, this means the correct containers must be placed in the correct locations, with labels and easy-to-follow instructions for disposal.

Understanding the Regulations

It’s one thing to comply with federal, state, and local regulations in principle; it’s another to demonstrate that compliance in a legal setting. In order to meet legal compliance requirements, a facility must obtain and keep track of training records, inspection documentation, incident reports, vendor information, and corrective action paperwork. These documents must also be completed to code and signed off on by the necessary parties. Compliance officers rely on the written record in addition to the practical examination of the facility, and incomplete paperwork can delay rulings or create mistrust even if everything is above board.

Don’t be fooled by generic national waste management checklists, they may seem helpful, but healthcare settings call for a more robust set of standards than a general checklist can provide. OSHA’s Bloodborne Pathogens standard must be consulted in cases of exposure to infectious materials, post-exposure protocols, and handling sharps. If any of the medical waste produced is classified as hazardous, then EPA requirements also come into play. Transportation is also regulated, and although it may vary by jurisdiction, it must often comply with DOT requirements.

Segregation and Containment

Medical organizations are hectic and busy by nature, but this is no excuse for ignoring or rushing through waste segregation. There is no reason for a waste item to remain in a work area outside of its container for any reasonable length of time, and any instance of this immediately puts the facility at risk. Every staff member should be properly trained on the four categories of waste they will encounter at the facility: healthcare waste, sharps, pharmaceuticals, and general waste, as well as how to handle and segregate waste the moment it’s produced.

Set the staff up for success by placing sharps containers where they’re needed, with a visible fill line and instructions, as well as regular monitoring of both rigid containers and bags for every type of waste. Safety officers must also watch out for unlabeled receptacles, containers moved to undesignated spots for convenience, loose items beside bins, or patterns of staff choosing the nearest container instead of the correct one.

Safe Handling and Storage

Restrictive signage expressly forbidding anyone but authorized staff from entering waste-storage areas is the first line of defense against hazardous exposure following disposal. The second is appropriate personal protective equipment (PPE) for the staff that is permitted to collect, transport, store, or clean around medical waste receptacles. Policy should ensure the layout allows staff to clean between waste-area surfaces and prevents cross-contamination between different waste streams. Supervisors must verify these details during routine inspections. Spill kits, emergency contacts, and instructions should be easily accessible to staff at all times.

When a problem arises, there must be a clear chain of command in place, and staff members must understand at what point they are to stop work and escalate it to a supervisor or another employee. Finally, training should not only include this information, but also provide an explanation for the why; otherwise, the process may feel arbitrary and lead to less retention and application.

Treatment and Disposal

Compliance doesn’t end when waste leaves the premises, and since waste treatment is outsourced, facilities must verify where the waste is going and what type of treatment it will undergo or face further penalties. Incineration is appropriate for certain materials, but it also produces emissions and requires specific permits. Autoclaving uses steam sterilization and therefore reduces microbial contamination but is not suitable for pathological or chemotherapy waste, nor can it be used on anything that can melt and emit fumes. Chemical treatment and microwave systems are also useful in specific settings, but all these methods must be compliant and produce clear documentation trails in order to be approved. Medical organizations should work with service providers that employ compliant processes, hold the necessary permits, and have contingency plans in place.

Working With a Medical Waste Disposal Company

Selecting a suitable medical waste disposal provider involves verifying that every step of the process will be documented, including waste collection, any required treatment, and final disposal. A reputable provider will take the time to explain its permits, treatments, transportation, staff training, documentation practices, and plans for service disruptions, and won’t balk at questions posed by the facility during the initial consultation.

The final decision on pickup frequency and waste container type should be a collaboration between the provider and the facility, with changes in waste volume, emergencies, or operational changes being part of an ongoing dialogue. Healthcare organizations should also look into the waste company’s references and performance data to see how they perform, since a contract will not reveal this information. If accountability seems vague, transportation is unreliable, or documentation is incomplete, it is best to continue looking for another waste removal company, even if their prices are competitive. Low prices are not a guarantee of good service, and when a company’s prices seem “too good to be true,” they often are.

Staff Training

A facility’s waste disposal system touches every part of an organization and therefore must be part of training for every type of staff member. Because waste management is so crucial to the environmental health of the building, every department must work together to ensure compliance and avoid small mistakes that can snowball into habit. Team members should feel comfortable reporting when waste isn’t handled appropriately, a container is damaged, or a pickup is missed, not feel guilty or uncomfortable. To facilitate this, team leaders should foster a strong safety culture by making reporting easy and low pressure. It’s imperative that supervisors respond with understanding rather than from a place of blame, investigate what conditions led to the event, and communicate the next steps to the appropriate parties with clarity. Reporting that leads to practical changes that can be seen every day results in staff that is more likely to participate in prevention.

Training new hires begins with online modules that cover every facet of the waste disposal process and the duties specific to their position, but competency checks are what keep whole teams sharp and able to apply these concepts to real-world scenarios.

Documentation and Inspections

The best way to prepare for an outside audit is to perform internal ones routinely, with a focus on the design of the overall on-site waste handling system. The workload, equipment, and communication systems should also be evaluated, and observable issues should lead to practical, ongoing improvements. These improvements should be monitored for efficacy and updated or implemented in other locations based on the data. Key points of focus should be examining work areas, storage of waste, staff training, vendor documentation, and the consequences of earlier findings.

By tracking waste volumes by type, pickup frequency, container use, incidents, and exceptions, a facility can catch a compliance issue before an inspector does. For example, if regulated waste volume suddenly increases, it may mean medical waste was mixed in at some point, or if containers are consistently overflowing, pickups are likely scheduled at the wrong frequency. Routinely reviewing these types of patterns helps management take concrete action in advance of an inspection that could result in costly fines and reputational loss. Documenting whether any corrective actions changed the process for the better is also helpful when applying for funding to make further improvements down the line.

Balancing Cost and Safety

Cost and safety often go hand in hand, but both can be compromised when an organization takes shortcuts in an attempt to save money. Consider a facility that puts an overflow of medical waste into the general waste stream. Not only are they compromising the safety of countless people down the line, but they’re likely increasing their general waste cost, poisoning their own data for future audits, and risking fines that would far exceed the cost of a proper disposal service. Not to mention potential lawsuits from needlestick injuries.

Rather than guessing at where to cut corners, medical organizations should instead record waste volumes, service types and frequencies, and incident reports so they can get a clear picture of where financial losses are occurring. Improper waste handling is more often a cause than it is a solution, and the documentation will likely reveal that fact.

Proper container selection, vendors that consolidate services, properly segregated waste, and contracts with providers that reflect actual patterns of waste generation are genuine improvements that may end up paying for themselves. It may be tempting to invest in the latest technology for training and maintenance, but management must assess whether the investment is likely to produce a return or is just serving to keep up the appearance of progress.

Small Steps Forward

Small tangible adjustments to behavior and equipment create greater lasting change than sweeping overhauls. Simplifying where waste receptacles are placed, removing improper containers, making the labels clear, conducting regular observations, and observing incident trends to inform retraining efforts all lead to gradual improvement over time. These improvements should all go hand in hand with relevant training for the appropriate staff, tailored to each individual’s position. Management should also continually reassess vendor relationships to ensure that their contracts are still followed and ongoing performance is up to par.

Waste volume increasing while storage and pickup schedules remain unchanged, and improper segregation of waste are larger issues that must be addressed before the situation goes on unnoticed for weeks, creating a genuine hazard. Sending regulated waste into general waste streams poses a risk to both human and environmental health, so keeping it separated is paramount.

A Complete System

Waste management is no less important than other operational functions and must be treated as such by medical organizations. Beginning with clear expectations will set the staff up for success and ensure every team member understands their role in waste-handling safety. When services expand, contract, or become modified in any way, procedures should be reviewed again to eliminate gaps in comprehension.

A successful waste management program connects infection prevention, environmental safeguards, and general facilities management to create a system that keeps people safe and quotas met.


Author Bio:

Rose Cartwright is an author and blogger whose work explores recycling, sustainability, and environmental science. When not writing, she can be found riding her horse, Chestnut, or facilitating creek cleanup initiatives in her hometown of Ithaca, New York.


Please also review AIHCP’s Managed Health Care Certification program and CE courses see if it meets your academic and professional goals.  These programs are online and independent study and open to qualified professionals seeking a four year certification

Can Preventive Care Be Too Fragmented to Work?

Discussion about treatment results

Written by Ryan Harris,

You can do everything you’re supposed to do and still not know whether anyone has looked at the whole picture.

They had the physical. They got the bloodwork. Maybe they saw a cardiologist, scheduled the mammogram, had a skin check, and finally followed through on that referral from last year. Ask what all those appointments added up to, though, and the answer may be harder to find.

The trouble usually isn’t a complete lack of care. It’s that the care happened in pieces. Different offices saw different parts of the story, at different times, in different systems.

That can leave a patient with plenty of medical activity but no obvious plan.

When separate appointments stop adding up

Specialists are part of good care. The problem is that each specialist is working from a narrower part of the record, while primary care may not have every result in front of them.

Sometimes the patient ends up filling the gaps, repeating the history at each visit and trying to remember which office has which result.

Picture a fairly common sequence. A primary care doctor notices something in routine bloodwork and recommends additional testing. The test is performed at an outside facility. A specialist reviews one part of it three weeks later. Another result lands in a patient portal without much context. By the next primary care visit, several people may have touched the case, but the information can still be sitting in separate records.

For someone who has trouble fitting several appointments into a workweek, a comprehensive executive physical can put imaging, lab work, physical testing, and physician review into a single visit. The useful part isn’t simply doing more tests in less time. It’s having the results considered together rather than arriving as disconnected pieces over several months.

AHRQ has documented how communication problems in outpatient care can create safety issues. Its work on patient safety in ambulatory care covers practical risks around referrals, medication information, test results, and follow-up when several people are involved in the same patient’s care.

AIHCP’s overview of the health care delivery system also shows how many parts sit behind a single visit. Records, referrals, facilities, payment, and follow-up all have to connect well enough for the next clinician to know what has already happened.

The problems are often small enough that they don’t look important at first. A medication list is outdated in one chart. A specialist asks for a scan the patient assumed had already been sent. Two doctors order similar blood tests because neither can see the other’s recent results. A referral is placed, but no appointment is ever made.

One missed handoff probably won’t unravel a person’s preventive care. Several of them can.

More testing can create its own kind of confusion

One response to fragmented care is to order more tests, hoping a larger set of results will provide a clearer answer.

More testing can help in the right situation, but it can also leave the patient with a larger pile of results that still need interpretation.

Screening also depends heavily on the person being screened. The U.S. Preventive Services Task Force changes recommendations based on age, sex, smoking history, pregnancy status, and other risk factors, so the same test may be appropriate for one patient and unnecessary for another.

Consider two 48-year-olds. One has a family history of early heart disease, rising blood pressure, and metabolic markers that have been moving in the wrong direction. The other has none of those issues but is overdue for routine cancer screening. Giving both the same giant checklist of tests may look thorough, but it doesn’t necessarily make either person’s care more thoughtful.

The reverse happens too. Someone gets a basic lab panel, sees mostly normal numbers, and takes that as evidence that everything important has been covered. An age-appropriate screening may still be overdue, or a follow-up recommended last year may never have been scheduled.

A test has limited value if nobody reviews what it changes about the patient’s care.

One result rarely settles the question by itself. A mildly abnormal number that has been stable for years may be less concerning than a result still inside the reference range but moving quickly. Medications, symptoms, family history, weight changes, earlier imaging, and new diagnoses all affect how a clinician interprets the number.

That is easier to judge when the clinician can see the previous results and the surrounding history instead of opening one portal at a time.

Otherwise, the patient may leave with a long list of results but no clear sense of what needs attention.

The six-month follow-up is often more important than the February physical

Say a patient has a routine physical in February and their cholesterol is higher than it was last year. The doctor suggests a few changes and asks for another lab test in six months.

Life moves on.

In April, the patient goes to urgent care for something unrelated. In June, a cardiologist gets involved because of family history. August comes around, but the repeat test isn’t on anyone’s calendar. The patient assumes the cardiologist is watching the issue. The cardiologist thought primary care was handling it. Primary care is waiting for the patient to schedule the lab.

There was no dramatic failure. Nobody ignored an emergency. A fairly ordinary follow-up simply fell into the space between offices.

By itself, that missed repeat test may not seem serious, but it means the original plan was never completed.

AHRQ defines care coordination around organizing care and sharing information among the people involved. In practice, that can be as basic as checking whether a referral happened, reading the specialist’s note, confirming repeat labs were completed, and deciding which clinician is responsible for follow-up.

AIHCP’s discussion of case management and utilization review deals with similar questions from a professional perspective. Completing the appointment is only part of the job. Someone still needs to check what came out of it, whether another step is due, and who is meant to handle it.

Patients feel the difference immediately.

“Your labs look mostly fine” isn’t much of a plan.

“Your blood pressure looks good, your cholesterol needs another check in September, and you’re still due for the screening we discussed last year” is something a person can act on.

The second conversation doesn’t require more technology or a more expensive test. It requires someone to keep track of the unfinished business.

Patients shouldn’t have to coordinate everything themselves

Being an engaged patient helps. In practice, that may mean carrying an updated medication list, knowing the important parts of your family history, keeping major reports handy, and asking what needs to happen after the visit.

But patients shouldn’t have to chase every record, referral, and result themselves just to keep the process moving.

With several clinicians involved, the administrative work adds up quickly. One portal holds the lab work. One office asks for the actual scan instead of the written report. Another needs the name and dose of a prescription from a different system. A referral may also sit in limbo until the patient notices that no one ever called.

Most people are managing this on top of work and family. A nonurgent lab or referral can disappear from the to-do list for months.

That is often how a six-month follow-up turns into a twelve-month one.

Better coordination doesn’t depend on every provider using the same software. Smaller workflow choices can close plenty of gaps. Schedule repeat testing before the patient leaves. Confirm that an outside report reached the chart. Before ordering a repeat test, check the recent record first. If a specialist is involved, the patient should also know whether that office or primary care is supposed to follow the result.

The last minute of the visit matters more than it sounds. “Come back if anything changes” doesn’t tell a patient whether anyone is expecting a repeat test, a call, or a return appointment. “Repeat this in six months, and our office will review the result with you” gives them a date, an action, and a clear owner.

AIHCP’s discussion of healthcare resource management is relevant here because wasted resources are not limited to budgets or staffing. Repeated tests, missing reports, and avoidable calls also use clinician time and patient time without necessarily improving care.

Care will still be spread across different places. A primary care office may use an outside lab, a hospital may handle imaging, and a specialist may keep a separate record. The practical question is whether the next clinician can see enough of that history to avoid starting over.

The patient shouldn’t have to rebuild that history from memory at every appointment.

Wrap-up takeaway

Preventive care starts to lose value when each appointment is treated as a separate event. Sometimes the test was done, but the result never made it back to the clinician who was supposed to act on it. Follow-up deserves as much attention as the screening itself. Patients can help by keeping copies of important reports and asking who is responsible for the next step, but the system still needs to do its share of the tracking. If several doctors are involved, it should be clear which office is watching each unresolved issue. Today, pull up your last physical or specialist note and check whether any repeat lab, referral, or screening was recommended without a date or a named person responsible for following it.

Author’s Bio

Ryan Harris writes about preventive health, longevity, and the changing role of diagnostics in modern healthcare. His work looks at how earlier risk detection, better health data, and more comprehensive assessments can help people make more informed decisions about their long-term health.


When the Hospital Is Hundreds of Miles Away: The Complexities of Medical Transport 

Speeding ambulanceWritten by Marchelle Abrahams,

The search for a missing air ambulance drew widespread news coverage over the weekend. A medical crew was reportedly transporting a patient and a family member from Bermuda to Boston when the plane went missing off the coast of Nantucket Island.

The unfortunate incident has left many questions unanswered, including how an aircraft could disappear moments after losing contact with air traffic control. 

And the 800-pound gorilla that hospital case managers are wondering about: transporting patients is a complicated web of safety and protocol. Where were the weak spots?

Answers remain vague, but that doesn’t discount the fact that medical transportation is a complex system that becomes even more intricate when the hospital is states away.


The Growing Need for Medical Transport

An aging population, rising rates of chronic illness, and a push to reduce missed medical appointments are part of the demand.

They’re also why the U.S. non-emergency medical transportation (NEMT) market is expected to grow to $13.43 billion by 2031, according to Research and Markets data.

NEMT providers serve Medicaid beneficiaries and patients in need of transportation to medical facilities for regular appointments and check-ups. Ambulance services, wheelchair assistance, stretcher services, flight services, and courier services are included.

However, working in healthcare gives us a bird’s-eye view of the challenges. Hospital case managers are probably the ones to witness this firsthand.

Inflation and operating costs leave many providers feeling squeezed, particularly in rural regions. The industry continues to face hurdles related to administrative complexity, broker dependencies, and compliance.

But we’re seeing some improvement. Strategy & Stats reports that collaborations among hospitals, private air medical transport companies, and insurers are improving coordination of patient transfer services and increasing access to air transportation services.


When Specialist Care Crosses State Lines 

Interstate medical transportation isn’t as cut-and-dry as transporting a patient and being done with it. Well, that’s what the general public thinks.

When it comes to medical transportation between states, providers must navigate a patchwork of federal rules, insurance policies, and operational scopes. There’s no single universal long-distance law dealing with interstate patient transport.

Hospital case managers and discharge planners usually handle the logistics of long-distance hospital transport. Discharge planning alone requires mountains of admin work. ACC Medlink suggests enlisting a professional, reliable transport partner that can provide documentation support.


The Role of Case Managers in Patient Transfers 

Nurse case managers are the unsung busy bees working behind the scenes. You ensure a patient’s transfer is safe, smooth, and continuous across care settings.

You evaluate the patient’s physical status, monitor vital signs, and decide whether the patient is stable enough for movement.

Probably your most underestimated role is advocating for your patient. You explain the inner workings of transferring them from one hospital to another facility and provide a vital link between them and their care team.

“During the 1960s and in subsequent decades, a growing patient rights movement embraced the importance of informed consent for honoring patients’ autonomy. Patient advocates arose as an important voice in this movement by educating patients about their rights and helping them participate more fully in decisions about their healthcare.” – Jennifer Schlinger, Clinical Associate Professor of Social Work, via The Conversation.


Access Barriers

Delayed care will remain a moot point as long as access to medical transport is only reserved for those who can afford it.

A 2024 review published in the Journal of Transport & Health paints a multifaceted picture. People in rural communities have to travel long distances to access healthcare services. The link between distance and/or travel time and healthcare service access hasn’t always been clear. 

The research looked at how distance and travel time affect access to healthcare for people living in rural and remote areas of developed countries. It found that travel time may be a better measure of healthcare access than distance, particularly for people living outside major cities.


FAQs

What is medical transportation between states?

Medical transportation between states refers to moving a patient across state lines to access healthcare. Depending on the patient’s condition, this can involve ground ambulances, non-emergency medical transportation, wheelchair or stretcher services, or medical flights.

Who arranges interstate medical transportation?

Hospital case managers, discharge planners, and healthcare teams often coordinate patient transfers. They may need to assess the patient’s medical needs, communicate with the receiving facility, arrange transportation, and ensure the necessary documentation is in place.

Why might a patient need to travel to another state for medical care?

Patients may need to cross state lines when specialized treatment is unavailable locally. This can include specialist consultations, advanced procedures, rehabilitation, transplant services, or treatment at a facility with specific expertise.

Is medical transportation between states covered by insurance?

Interstate medical transportation coverage depends on the patient’s insurance plan, medical needs, and the type of transportation required. Medicaid and private insurers may have specific eligibility and authorization requirements, so patients and care teams should confirm coverage before arranging transportation.


Medical Transportation: Key Stats 

Stat What it Tells Us
$13.43 billion Projected value of the U.S. non-emergency medical transportation market by 2031 
Travel time vs. distance Research suggests travel time may provide a better picture of healthcare access than distance alone
Cross-state transfers Interstate transfers can involve coordination between hospitals, insurers, transport providers, and healthcare professionals
Multiple transport options NEMT can include ambulances, wheelchair transport, stretcher services, medical flights, and courier services


Getting Patients There Is Part of the Care 

Healthcare doesn’t end when a patient leaves one hospital. Transporting them to the next facility is just as important. We may not know what happened on that fateful air ambulance flight.

But we do know it doesn’t define the NEMT industry. Yes, challenges remain top of mind, yet every case manager’s goal is to get patients from point A to point B with as few complications as possible.

Author bio

Writer by day, dream catcher by night. Marchelle Abrahams cut her teeth in the infancy of the internet when the dial-up sound of the modem was more than a soundbite at a rave. Not a Millennial and not a Boomer, Marchelle is an in-betweener, making her a special breed of human. As a qualified journalist, Marchelle believes her superpower is stringing a few words together and people reading them.


References:

Search suspended for missing Ontario-based air ambulance with four Canadians aboard : U.S. Coast Guard. (2026, October 5). Nationalpost. https://nationalpost.com/news/four-canadians-aboard-ontario-based-air-ambulance-missing-off-u-s-coast 

Ltd, R. a. M. (n.d.). US Non-Emergency Medical Transportation Market Size & Trends. Research and Markets Ltd 2026. https://www.researchandmarkets.com/report/united-states-non-emergency-medical-transportation-market 

Kardani, P. (2026, October 7). U.S. air ambulance services industry: emergency care insights. SNS Insider. https://www.snsinsider.com/blogs/air-ambulance-services-industry 

Schlinger, J. (n.d.). What is a professional patient advocate, and why might you need one? The Conversation. https://theconversation.com/what-is-a-professional-patient-advocate-and-why-might-you-need-one-281971 

Impact of distance and/or travel time on healthcare service access in rural and remote areas: A scoping review. Journal of Transport & Health July 2024. https://www.sciencedirect.com/science/article/pii/S2214140524000653 

Us, J. K. W. (2026, October 5). A surgeon shortage creates challenges in rural communities. The Week US. https://theweek.com/health/a-surgeon-shortage-creates-challenges-in-rural-communities 

Please also review AIHCP’s Case Management Certification program and our CE courses as well, to see if they meet your academic and professional goals.  These programs are online and independent study and open to qualified professionals seeking a four year certification

Reduction, Not Only Abstinence: Meeting Patients in the “Gray Area” of Alcohol Use

drunk man drinking alcohol at table at night. Acceptable or in the gray area of alcohol use?

Most people whose drinking exceeds healthy limits will never walk into an addiction clinic. They are not dependent on alcohol, and they do not meet the criteria for a severe use disorder. Many are not looking for treatment at all. Their drinking is still not harmless, and a growing number of them know it. They sit in what clinicians and patients alike describe as a gray area: too much to ignore, not enough to resemble the treatment system as most people picture it.

The clinical term of art for this group is “unhealthy alcohol use.” The U.S. Preventive Services Task Force (USPSTF) defines it as a spectrum of behaviors that runs from risky drinking to alcohol use disorder. Risky or hazardous drinking means drinking above recommended limits, in a pattern that raises the risk of health consequences without meeting the criteria for an alcohol use disorder. An alcohol use disorder is a different matter: a medical condition in which a person struggles to stop or control drinking despite the consequences, and it can be mild, moderate, or severe.

The distinction shapes how care is organized. A person who drinks above the limits but has no disorder is unlikely to accept, or need, an abstinence-only pathway. A person with a severe disorder needs much more than a brief conversation. Between those poles lies a large, quiet group that the health system mostly misses.

Why this group is easy to miss

People who drink in the gray area rarely describe themselves as having a problem. Popular culture still draws a hard line between “alcoholics” and everyone else, and that framing can work against early change: when cutting back reads as an admission of a problem, reluctance to try tends to grow. Research documents a second barrier. A scoping review led by clinical psychologist Devin Banks found that Black people in substance use treatment feared being judged by employers, police, and others, and that this stigma can be a barrier to treatment.

Drinking to cope is also normalized. About two-thirds of adults in the United States report drinking in the past year, and nearly a quarter report binge drinking in the past month. When a drink is how someone marks the end of a workday, cutting back is less a medical decision than a social and personal one.

The scale of the harm justifies attention. Excessive alcohol use is one of the most common causes of premature death in the United States; the Task Force cites an estimated 88,000 alcohol-attributable deaths a year from 2006 to 2010, from acute causes such as injuries and from chronic conditions such as liver disease.

What the evidence supports

Screening for unhealthy alcohol use in primary care, followed by brief behavioral counseling for patients who screen positive, carries the Task Force’s Grade B recommendation for adults 18 and older, including pregnant women. The Task Force concluded with moderate certainty that the net benefit is moderate. For adolescents aged 12 to 17, the evidence remains insufficient to weigh benefits against harms.

The benefit is real but not dramatic, and the numbers are worth knowing. Pooled trial results behind the recommendation show that brief counseling reduced the odds that a patient would exceed recommended drinking limits by roughly 40 percent (odds ratio 0.60; 95% CI, 0.53 to 0.67), and lowered the odds of a heavy-use episode by about a third, with outcomes measured at 6 to 12 months. The Task Force also bounded the harms of screening and brief counseling as small to none.

Two details keep the picture honest. The interventions that worked varied in their components, administration, length, and number of interactions, and the Task Force could not identify which characteristics were clearly associated with better outcomes; the conversation matters more than any fixed script. Part of the case for reduction also rests on indirect evidence: epidemiologic studies link reductions in drinking with lower risks of illness and death, even though they cannot show that a brief conversation produced the change on its own.

External assessments point in the same direction. The World Health Organization (WHO) has concluded that no level of alcohol consumption is safe for health, that alcohol causes at least seven types of cancer, and that risks start from the first drop of any alcoholic drink; as one WHO official puts it, the less you drink, the safer it is. A reduction-focused conversation does not have to settle debates about safe levels. It only has to help someone move in the safer direction.

The service model that carries this into practice is SBIRT: screening, brief intervention, and referral to treatment. The Substance Abuse and Mental Health Services Administration (SAMHSA) describes SBIRT as a public health approach to delivering early intervention and treatment services in primary care centers, hospital emergency rooms, trauma centers, and other community settings: a quick screen assesses the severity of use, a brief intervention builds insight and motivation toward change, and a referral pathway connects people who need more to specialty care.

What this looks like in practice

Whatever your role, you are better positioned than you may think. Nurses notice patterns at intake. Case managers hear how the week actually went. Chaplains and counselors sit with the stress that drinking is often managing. None of these roles requires prescribing authority, and none requires a full clinical assessment to be useful.

Screening can be short. One- to three-item instruments such as the AUDIT-C and the single alcohol screening question have the best accuracy for detecting unhealthy alcohol use in adults, and the AUDIT-C takes a minute or two to administer.

When someone screens positive, the brief intervention is a conversation rather than a lecture. In SAMHSA’s description, it works by increasing a person’s insight and awareness about their substance use and their motivation toward change. Cutting back and stopping altogether are both defensible goals; the evidence behind reduction-focused care is what makes it reasonable to support someone who is not ready to quit. People can take smaller steps toward health even when they are not ready for permanent abstinence. For patients who want structured support between visits, patient-facing programs such as Sunnyside offer app-based tracking, coaching, and clinician-supervised options for those who want to reduce. Programs like this work alongside clinical care, not in place of it, and they are one option among many a patient can weigh.

Language does quiet work here. “Alcoholic” remains a stigmatizing term, and the sober curiosity framing works partly by setting the label aside: anyone can try cutting back, without having to define themselves as a problem drinker first. And when a cutback attempt fails, that failure is information: practitioners in this space treat it as a signal that a plan, a goal, or a support level needs adjusting, not as proof that the person cannot change.

When moderation is not the right goal

Reduction-focused care has a safety boundary, and it is not optional. Moderation is not an appropriate goal for someone with a physical dependence on alcohol. Withdrawal in that situation can be fatal, and patients who become nauseated, shaky, or otherwise unwell when they try to cut back need supervised medical withdrawal rather than a self-guided plan. Some of those patients might be better off seeking permanent abstinence, and others need formal treatment; the treatment navigator listed below exists for that handoff. The screening recommendation itself is written for people who are not already in evaluation or treatment for alcohol problems.

Pregnancy is its own case: alcohol use during pregnancy is one of the major preventable causes of birth defects and developmental disabilities, and brief counseling increased the likelihood that women remained abstinent from alcohol during pregnancy.

The takeaway for practice

The next step for any role in this work is a small one. Screen when you can, and let the screening become a conversation about goals rather than a verdict about drinking. Treat reduction as a legitimate goal for patients who are not ready for abstinence, and keep the safety boundary in view: withdrawal risk and pregnancy belong with clinicians, and a timely handoff is part of the care. That is the practice in its everyday form: a question, a conversation, a goal the patient chooses, and a clear line where clinical care takes over.

Resources to share with patients and clients

Two free NIAAA resources are worth knowing by name. Rethinking Drinking offers practical tools for adults who want to examine or cut back on their drinking, including strategies for cutting down and a free booklet. The NIAAA Alcohol Treatment Navigator is aimed at people who may need treatment for an alcohol use disorder; it focuses on evidence-based care, includes questions to ask a potential provider, and carries no commercial sponsorship.


Author’s Bio:

This article is brought to you by the expert content team at nexuse backlinks agency, specializing in digital marketing, SEO, and quality online resources


Please also review AIHCP’s Substance Abuse Practitioner Program and  CE courses to see if it meets your academic and professional goals.