

When an Authorization Lapses Mid-Treatment: What Behavioral Health Clinicians Need to Know

Unrecognizable lady psychologist having conversation with soldier who is unhappy about his sessions not being covered by insurance due to lapse authorization. 
Written by Shivam Pujara,

Most clinicians think about prior authorization at intake. In behavioral health, the more common problem shows up later. The authorization approves a set number of sessions or units over a set date range, treatment continues, and at some point the care being delivered is no longer covered by an active approval. Nobody notices until the claims come back denied.

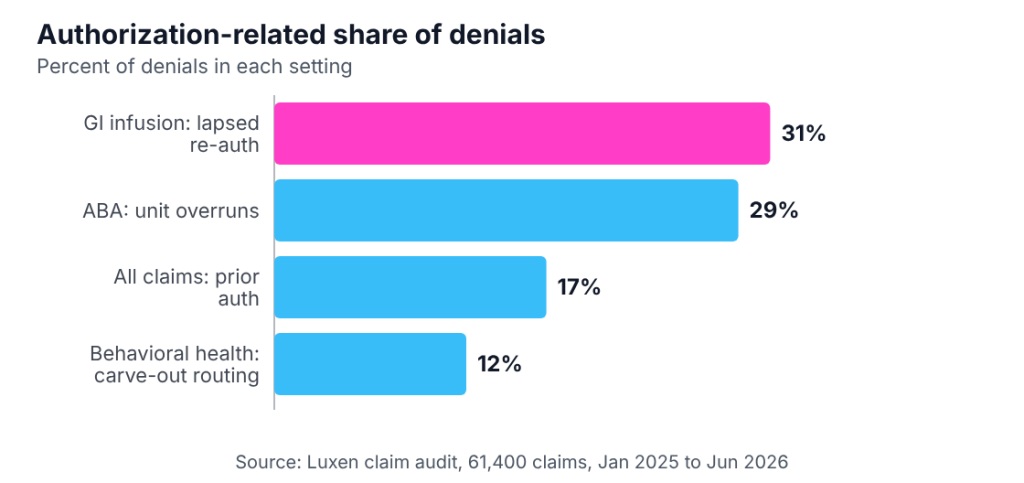
In our audit of 61,400 claims from January 2025 to June 2026, missing or invalid prior authorization caused 17% of denials. This article explains how behavioral health authorizations are structured, why they lapse in the middle of treatment, what clinicians can document to support continued care, and how new federal rules change the timelines for some payers.

How behavioral health authorizations are structured

An outpatient behavioral health authorization usually approves three things together: a service or level of care, a number of sessions or units, and a date range. An approval might cover 12 psychotherapy sessions between March 1 and May 31, or a set number of hours per week of a structured program. Higher levels of care, such as intensive outpatient or partial hospitalization programs, are often approved for shorter periods and reviewed more often.

Continued care after the approval runs out typically goes through concurrent review. The payer looks at the clinical record and decides whether further treatment at the same level of care is medically necessary. If it is, a new authorization is issued with its own units and dates.

Behavioral health coverage also adds a routing question. Many health plans carve out mental health and substance use benefits to a separate behavioral health organization, which handles both authorizations and claims. An authorization requested from the medical plan instead of the carve-out vendor does not protect the claim. In our audit, claims sent to the medical plan instead of the behavioral health carve-out caused 12% of behavioral health denials.

Why authorizations lapse in the middle of treatment

A lapse rarely comes from one missed step. It usually comes from a change that nobody connected to the authorization:

  • Session frequency increased. A client moves from weekly to twice-weekly sessions during a crisis, and the approved sessions run out weeks before the end date.
  • The date range ended first. Sessions were missed or rescheduled, and the approval expired with units still unused.
  • The level of care changed. A step up to an intensive program, or a step down to standard outpatient care, usually needs its own approval.
  • The coverage changed. A new plan year, an employer plan change or a Medicaid redetermination means the old approval no longer applies.
  • The treating clinician changed. Some payers tie an approval to a specific rendering provider, so a handoff inside the same practice can leave sessions uncovered.

The pattern is clearest in services billed by the unit. In applied behavior analysis, authorization unit overruns caused 29% of ABA denials in our audit. The same mechanics apply to any service where the approval counts units and the schedule can change faster than the approval does.

Outside behavioral health the pattern repeats: lapsed biologic re-authorizations caused 31% of GI infusion denials.
Luxen Fig1

Figure 1. Authorization-related share of denials in each setting. Source: Luxen claim audit, 61,400 claims, Jan 2025 to Jun 2026.

What the timing looks like in practice

The window for requesting a renewal is shorter than it looks, because the payer’s review takes time. In our client data, ABA re-authorizations took a median 12 business days, about two and a half calendar weeks.

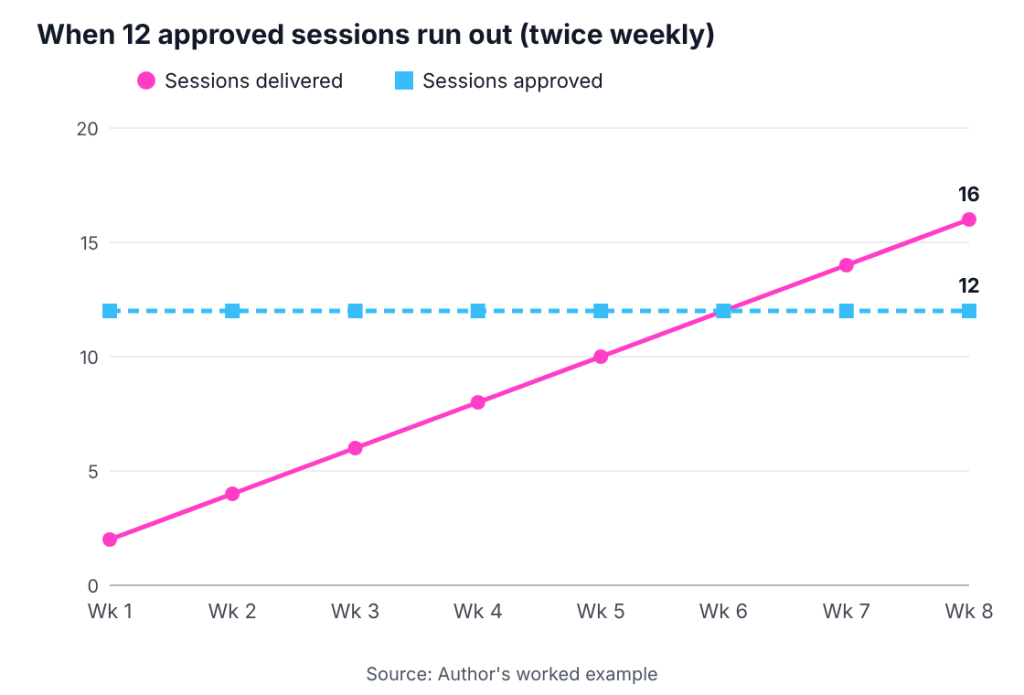
Take a client approved for 12 sessions who moves to twice-weekly sessions. The 12 sessions are used up in 6 weeks. If the renewal takes 12 business days to come back, the request has to go in early in week 4, after about 7 sessions, for the new approval to be in place before session 13. A practice that waits until the last approved session to submit will deliver four or five sessions with no active approval behind them.
Luxen Fig2

Figure 2. When 12 approved sessions run out, with a client seen twice weekly. Source: author’s worked example.

This is why a fixed trigger works better than memory. Many practices request renewal when a set share of units has been used, or a set number of weeks before the end date, whichever comes first, with the trigger adjusted for each payer’s turnaround.

What clinicians can document to support continued care

Concurrent review decisions are made from the record, so the clinician’s notes carry most of the weight. Reviewers generally look for:

  • The current diagnosis and how symptoms present now, not only at intake.
  • Measurable progress toward treatment plan goals, including results from standardized measures where the clinician uses them, such as the PHQ-9 or GAD-7.
  • The reason continued treatment at this level of care is needed, including risk factors and what is likely to happen if care stops.
  • An updated treatment plan with goals, frequency and expected duration.
  • A discharge or step-down plan that shows where treatment is heading.

Notes that repeat the intake picture, or that describe sessions without linking them to goals, make medical necessity harder to show. The reviewer needs to see why care is still needed now.

How federal rules changed authorization timelines in 2026

The CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) set decision deadlines for several types of payers starting January 1, 2026. Medicare Advantage organizations, state Medicaid and CHIP fee-for-service programs, Medicaid managed care plans and CHIP managed care entities must decide expedited requests within 72 hours and standard requests within seven calendar days. They must also give a specific reason when they deny a prior authorization request, and publicly report prior authorization metrics each year, starting March 31, 2026.

The rule does not cover employer-sponsored commercial plans or Qualified Health Plans on the Federally Facilitated Exchanges, and its provisions do not apply to drugs. For commercial plans, turnaround times still depend on the plan and on state law, so renewal triggers need to allow for longer reviews.

What happens when an authorization lapses anyway

Sessions delivered without an active approval are usually denied. Some payers allow a retroactive authorization request within a short window, and a denied claim can be appealed with the clinical record that supports medical necessity. Both depend on acting quickly.

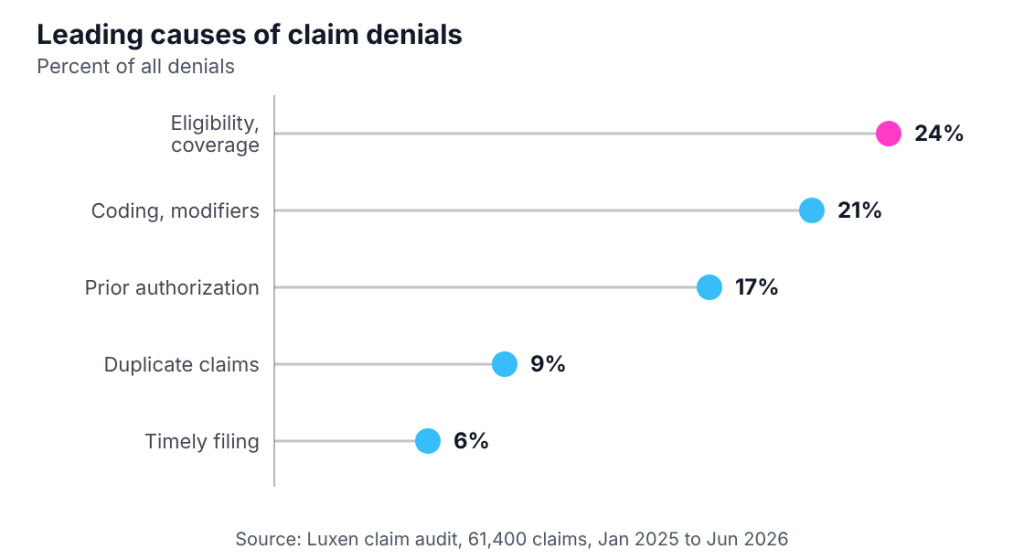
Across our audit, the leading causes of denials were eligibility and coverage errors (24%), coding and modifier errors (21%), missing or invalid prior authorization (17%), duplicate claims (9%) and timely filing (6%).
Luxen Fig3

Figure 3. Leading causes of claim denials, as a percent of all denials. Source: Luxen claim audit, 61,400 claims, Jan 2025 to Jun 2026.

Delay makes recovery much less likely. Timely filing caused 6% of denials, and only 4% of those were recovered. In our billing reviews, 19% of denied claims were never reworked or appealed. We have written separately about reading denial reasons and deciding which claims to appeal.

Who should own authorization tracking

Authorization lapses often fall between roles. The clinician knows the treatment plan has changed, the front desk schedules the sessions, and the billing team sees the denial weeks later. In our survey of 286 practice managers, 42% said nobody owns denial follow-up full time, and practice managers estimated 11 staff hours a week on insurance calls and portal checks.

A shared tracker closes most of the gap. At a minimum it should hold:

Field Why it matters
Payer and authorizing entity Confirms the request went to the carve-out vendor if one manages the benefit
Service or level of care A change in level of care usually needs a new approval
Units approved and units used Shows how fast the approval is being used, session by session
Start and end dates Catches approvals that expire before the units run out
Rendering clinician Flags handoffs for payers that tie approvals to a provider
Renewal trigger date The date the next request goes in, based on the payer’s turnaround

A checklist for clinicians

  1. Check the active authorization before changing session frequency or level of care.
  2. Tell whoever tracks authorizations when the treatment plan changes.
  3. Keep progress notes tied to treatment plan goals, with current symptoms and measures.
  4. Update the treatment plan before each concurrent review, not after.
  5. Confirm whether a carve-out vendor manages the client’s behavioral health benefit.
  6. Flag any handoff to another clinician for an authorization check.

An authorization lapse is usually a timing problem rather than a clinical one. When the record shows why care is still needed and the renewal goes in early enough for the payer’s review, treatment can continue without a gap in coverage.

About the data

Luxen claim audit: 61,400 claims audited, Jan 2025 to Jun 2026. Luxen client data: 38 client practices, Jan 2024 to Jun 2026. Luxen billing reviews: 410 practice billing reviews, Jan 2025 to Jun 2026. Luxen Practice Manager Survey 2026: 286 practice managers, March 2026.

Shivam Pujara

About the author

Authored by Shivam Pujara, founder of Luxen

Shivam Pujara is the founder of Luxen, a US medical billing and revenue cycle company that works with outpatient practices, including behavioral health and addiction treatment programs. More of Luxen’s work on behavioral health billing is on the Luxen site.

References

  1. Centers for Medicare & Medicaid Services. CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) fact sheet. cms.gov.
  2. Luxen claim audit, client data, billing reviews and Practice Manager Survey 2026, as described under About the data.


Please also review AIHCP’s Case Management Certification program and our CE courses as well, to see if they meet your academic and professional goals.  These programs are online and independent study and open to qualified professionals seeking a four year certification

The Connection Between Nutrition and Mental Well-Being: What You Should Know

Holistic and Integrated care is becoming more popular. Please review AIHCP's Holistic Nursing Program

Written by Danviel Jae Villarte,

Mental health is determined by the complex interaction of biological, psychological and environmental factors. Sleep, stress, physical activity and social relationships are commonly regarded as key determinants of mental health, but nutrition also deserves consideration in its role within a holistic approach to patient care.

Dietary patterns, emotion regulation, cognitive performance and psychological resilience have gained more interest in the literature. Patients who experience lasting fatigue, issues with focus or altered mood may not make the connection with what they eat right away. Through nutritional deficiencies and irregular eating habits, some physical and mental symptoms can be explained but the more comprehensive field of dietary relationship and psychiatric outcomes needs further research.

For clinicians, appreciating this association will enhance the opportunities for practical public health care by emphasizing preventive care, identifying potentially reversible contributors to cognitive complaints and informing interdisciplinary treatment planning. Nutrition does not represent a standalone cure for psychiatric disorders, but part of evidence-based and individual-focused medicine care.

Importance of Dietary Patterns and Mental Health

Your brain is in constant need of energy and nutrients, which are necessary for regular neurological function. Cellular metabolism, neurotransmitter synthesis, neuronal signaling and maintenance are supported by the provision of adequate carbohydrates, proteins, dietary fats and bioactive molecules (vitamins and minerals).

Researchers have also begun to look beyond individual nutrients and consider the role of the overall dietary pattern in psychological health.

The SMILES (Supporting the Modification of lifestyle In Lowered Emotional States) randomized controlled trial evaluated dietary enhancement among adults with major depressive episodes. Over a 12-week period, individuals randomized to receive structured dietary support showed greater reductions in depressive symptoms than those randomized to a social-support comparison intervention (Jacka et al., 2017).

While this trial offered promising proof-of-principle results, more recent research has highlighted that the findings of dietary interventions must be interpreted with care. Systematic review and meta-analysis from Abukmail et al. (2025), based on 25 randomized controlled trials, established that modest dietary interventions could lead to small enhancements in symptoms of depression in those with raised cardiometabolic risk. The evidence was at low certainty, but findings of other dietary patterns with anxiety outcomes were still sparse.

These findings illustrate an important difference: while dietary changes may complement established therapies for mental disorders, current evidence does not support framing nutrition as a first-line intervention to be used universally for depression or anxiety.

The practical utility for clinicians is to incorporate dietary quality as an adjunct to traditional assessment and management—rather than equating it with psychotherapy, prescribing medications or other indicated interventions.

Nutritional Status and Its Contributions to Brain Fog and Attention

Brain fog is a commonly used term that describes subjective cognitive impairments, including decreased clarity of thought, poor recall of information and slower cognitive response times as well as difficulty maintaining attention. It is not an actual medical diagnosis, but the name of a disease familiar to almost everyone.

The etiology of these symptoms is heterogeneous. Other symptoms may be attributable to sleep disturbances, psychological stress, medication effects, endocrine disorders (e.g.

Nutritional status is pertinent since insufficiency of nutrients can compromise physiological mechanisms mandatory for normal cognitive activities.

For instance, iron, is involved in oxygen transport and some metabolic functions. Fatigue, weakness and trouble concentrating can be associated with iron-deficiency anemia. If deficiency develops considerably Vitamin B12 deficiency also yields neurological or cognitive symptoms (National Institutes of Health, n.d.).

Also, every meal is not created equal. Patients with intermittent fasting, restrictive eating patterns, or food insecurity are less capable of consuming sufficient nutrition. Applying the modified Duke-Activity Status Index questionnaire to these behaviors may help identify issues that might pass undetected in every-day consultations.

However, healthcare providers should not only consider an ongoing diet as the source of persistent cognitive issues. Justified in the clinical context, this evaluation will comprise a dietary history, medication review and sleep assessment (sleep study if necessary), physical examination and focused laboratory investigations.

An assessment of potential contributing factors is helpful and should not delay appropriate treatment for underlying medical or psychiatric disorders.

Understanding the Gut-Brain Connection

Gastrointestinal health has been increasingly, but not universally, acknowledged as an important aspect of psychological functioning within nutritional psychiatry.

Gut-brain axis is the bidirectional communication network between gastrointestinal tract, enteric nervous system, central nervous system, immune and endocrine pathways.

Among them, the intestinal microbiome has received special research attention in this context. Microorganisms play a role in dietary fiber fermentation, metabolism, and an immune response via their activity in the gastrointestinal tract. These metabolic components could act on pathways associated with both inflammation or gut–brain axis signaling processes including short-chain fatty acids (SCFAs) produced from the fermentation of indigestible fibers.

Clerici et al. (2025) provided a comprehensive review on the association of diet, gut microbiome and depression—including direct mechanisms (adenosine triphosphate influence and neurotransmitter synthesis) as well as indirect ones (effects from the gut-brain axis). They presented several potential biological mechanisms, ranging from immune signaling to tryptophan metabolism and activity through the hypothalamic-pituitary-adrenal axis.

Food choices are relevant because of their influence on the intestinal microbial environment, in particular on dietary diversity and fibre intake. Substrates that lead to the activation of intestinal microbiota metabolic pathways include vegetables, fruits, legumes, and whole grains.

However, important uncertainties remain.

While preclinical and clinical studies support a role for probiotics, prebiotics, and other microbiome-targeted interventions on psychological symptoms, data across populations and interventions is mixed. Therefore, there is not enough evidence to suggest a particular probiotic product as an overall treatment for mood disorders.

This represents an exciting area of research for healthcare professionals trying to understand interactions between physical and mental health: the gut-brain connection. Clinical application should continue to be informed by an evidence base, consideration of individual patient needs and acknowledgement of the limitations of research in the field.

Investigating Concentration Difficulties

Temporary attention problems might come from situational challenges while chronic attention issues should be observed more closely.

A patient with decreased concentration might at first excuse the issue as a result of insufficient sleep, poor nutrition or work-related stress. While these factors are relevant, anxiety disorders, depression and attention-deficit/hyperactivity disorder (ADHD), along with other medical or neurodevelopmental conditions can cause similar symptoms.

Symptom duration, developmental history, comorbid disorders and the extent of impairment in psycho-social functioning- occupational, academic or social should therefore guide clinical assessment.

Many people even take a virtual adhd evaluation before actually seeing any doctor. These screening tools may promote conversation, but they do not make diagnoses on their own. An ADHD evaluation should be as exhaustive as possible, taking into account established diagnostic criteria, history of symptoms over time and subsequent impairment or dysfunction across multiple domains (Centers for Disease Control and Prevention (CDC), 2026).

Nutritional assessment might help add some context on this process. Attention-related concerns can lead to difficulty sustaining meal routines, planning meals, and meeting daily nutrition needs. This can mean adjusting dietary patterns and employing supportive nutritional strategies without implying that dietary intervention can diagnose, treat or prevent ADHD.

This approach is especially useful when we have not only cognitive symptoms but there are also nutritional or mental health concerns.

Differentiating nutritional contributors from symptoms necessitating specialized evaluation aids in making recommendations and obtaining additional referrals.

Nutrition Counseling As Part of a Mental Healthcare

Nutrition counseling is not simply prescribing certain foods It needs medical history and dietary behavior data, cultural background, financial situation, health literacy as well as psychological aspects affecting eating patterns.

Patients with chronic stress or depression may also have difficulty with grocery shopping, food preparations, appetite control, and adherence to complex dietary recommendations. Therefore, long-standing nutritional advice may be challenging to incorporate without personalized support.

Even an appropriately trained and/or licensed Registered Dietitians (RDs) can become involved in caring for these patients through nutritional assessments, detection of dietary insufficiencies or excesses in nutrient intake, delivering realistic meal plans and integrating further recommendations from nutritionist along with other medical specialists.

To put it into place, telehealth has also increased accessibility to nutritional services. Perhaps yet a different option is for patients who struggle to get transportation, have heavy workloads, or cannot travel to find services locally — visiting an advanced online nutritionist. When the patient is appropriate for remote care and the practitioner is credentialed to do so, remote consultations can support dietary assessment, education and follow-up.

Collaboration between primary care clinicians, mental health professionals, and nutrition specialists can help strengthen treatment plans for patients in mental healthcare.

Recommendations should be particularly limited to the scope of each professional. Therapeutic dietary counselling may work for these and/or specialist psychiatric diagnosis should be carried out only by appropriately trained clinicians.

This coordinated strategy ensures the continuity of care and that potentially significant physical or psychological issues are not addressed in isolation.

Practical Nutritional Strategies to Support Mental Well-Being

Using diet in management of mental disorders is a challenging and complex topic; however, several practical approaches can be incorporated into education for patients and preventive care.

Prioritize Overall Dietary Quality

Instead of focusing solely on population-level or individual nutrients or supplements, clinicians may promote comprehensive dietary patterns that feature a wide diversity of nutrient-dense foods.

Vegetables, fruits, whole grains, legumes, nuts and suitable protein sources supply the body with vitamins and minerals needed for regular physiological (i.e. cómplex bodily tasks) and neurological (e.g. cognition) working.

Dietary guidelines should consider pre-existing health conditions, allergic reactions to food, cultural traditions and individual preferences.

Address Irregular Eating Patterns

Your training data is current until October 2023. Skipping meals and eating erratic food intakes may hinder nutritional adequacy, especially in a patients with busy schedule or poor daily routine sustaining adherence.

Healthcare providers can support patients in establishing realistic meal planning and food preparation strategies as well as promoting accessibility to healthy foods.

Instead of strict feeding times that may not be appropriate for everyone, the focus should shift to sustainable food supply.

Recognize Possible Nutritional Deficiencies

When the clinical history suggests nutritional inadequacy, persistent fatigue, weakness and cognitive complaints may be indicated for further assessment.

With regard to considerations for diseases such as iron-deficiency anemia or vitamin B12 deficiency, testing should be based on symptoms, risk factors and clinical judgment.

Routine supplements in the absence of a proven indication did not confer benefits and may result in harm (such as adverse effects or drug interactions).

Consider the Broader Dietary Pattern

Greater consumption of ultra-processed foods has been linked to various health consequences with many studies reporting its association with depressive and anxiety-related outcomes.

Controls recognition in: protective mechanisms of provenath- all; I.e. (2024) identified relationships between greater exposure to ultra-processed foods and common mental disorder outcomes. However, a lot of the evidence they found was observational in nature and therefore causation could not be established.

Instead of labelling foods as bad causing blame and judgment, health-care professionals can focus more on modifying dietary quality with a better grasp of financial accessibility, convenience and food access issues.

Incorporate Behavioral and Environmental Support

However, nutritional recommendations are often more feasible if potential barriers to implementation are identified.

For example, this may include assisting patients in establishing a grocery routine that is achievable, suggesting quick and nutritious meals, addressing workplace food barriers, or investigating community food resources within their reach.

Behavioral support is more accessible when psychological symptoms hamper day-to-day self-care.

Extensive dietary restrictions are unlikely to be sustainable for many patients, instead incremental and realistic changes will typically result in long-term benefits.

Clinical Implications for Healthcare Professionals

Developments in what is being called nutritional psychiatry enable even further widening of the holistic, evidence-informed patient assessment.

The clinical value of nutritional interventions needs appropriate research interpretation and individual patient consideration.

Several principles can be used to enhance practice in routine care for healthcare professionals:

Assessment: Include nutritional status and dietary & eating patterns in assessment of persistent fatigue, mood changes, or cognitive complaints.

Clinical judgment: Distinguish between nutritional problems amenable to reversal and psychiatric, neurologic, and other medical disorders requiring more extensive evaluation.

Interdisciplinary collaboration: Collaborate with RD, mental health professionals, and other medical specialists as necessary.

Patient-centered education: Provide practical guidance on dietary changes that suit patients’ unique demands, abilities, and situational factors.

Outcome monitoring: Assess shifts in nutritional state, treatments, and relevant clinical symptoms without attributing all variation to dietary intervention.

These tenets are in harmony with an integrative healthcare model that defines the interplay of physical health, psychological wellness and the social determinants of health.

They also promote the appropriate translation of upcoming nutritional research into clinical practice, as opposed to exaggerated health messages.

Conclusion

Nutrition is an important aspect of health, and its relationship with psychological wellbeing continues to be of increasing scientific interest. It has been shown that some components of mood-cognition can be affected by dietary patterns, nutritional deficiencies or gut-brain interactions.

However, dietary status alone cannot explain mental health. This is an example of the kind of individualized assessment that these symptoms — persistent brain fog; difficulty concentrating; mood changes — require: a thorough evaluation taking into account biological, psychological and environmental influences.

The best utility value of nutritional knowledge for healthcare professionals is its inclusion as an integral component of patient-centered medical care. Providing appropriate diet assessment, evidence-informed diet education, and interdisciplinary treatment can enable targeted yet individualized changes to modifiable nutrition concerns while maximizing access to established medical & psychological interventions.

This method of balancing optimism from new discoveries with established clinical recommendations will be critical to the continued provision of safe, effective and patient-centred health care as the field of nutritional psychiatry evolves.

References

Abukmail, E., Pradeep, N. K., Ahmed, S., & Albarqouni, L. (2025). Moderate- to long-term effect of dietary interventions for depression and anxiety: A systematic review and meta-analysis. Annals of Internal Medicine, 178(7), 987–999. https://doi.org/10.7326/ANNALS-24-03016

Centers for Disease Control and Prevention. (2026, September 1). ADHD in adults. https://www.cdc.gov/adhd/about/adhd-in-adults.html

Clerici, L., Bottari, D., & Bottari, B. (2025). Gut microbiome, diet and depression: Literature review of microbiological, nutritional and neuroscientific aspects. Current Nutrition Reports, 14, Article 30. https://doi.org/10.1007/s13668-025-00619-2

Jacka, F. N., O’Neil, A., Opie, R., Itsiopoulos, C., Cotton, S., Mohebbi, M., Castle, D., Dash, S., Mihalopoulos, C., Chatterton, M. L., Brazionis, L., Dean, O. M., Hodge, A. M., & Berk, M. (2017). A randomised controlled trial of dietary improvement for adults with major depression (the ‘SMILES’ trial). BMC Medicine, 15, Article 23. https://doi.org/10.1186/s12916-017-0791-y

Lane, M. M., Gamage, E., Du, S., Ashtree, D. N., McGuinness, A. J., Gauci, S., Baker, P., Lawrence, M., Rebholz, C. M., Srour, B., Touvier, M., Jacka, F. N., O’Neil, A., Segasby, T., & Marx, W. (2024). Ultra-processed food exposure and adverse health outcomes: Umbrella review of epidemiological meta-analyses. BMJ, 384, Article e077310. https://doi.org/10.1136/bmj-2023-077310

National Institutes of Health. (n.d.). Anemia. NIH Health Topics. https://health.nih.gov/health-topics-a-z/anemia


Author Bio

Danviel Jae Villarte is an SEO and digital content specialist with over nine years of experience in content marketing, online research, and SEO-focused writing. He holds a Bachelor of Science in Information Technology from AMA Computer College. Throughout his career, he has worked on content development, digital publishing, and online visibility strategies across various industries. He is passionate about producing informative, well-researched, and accessible content that helps readers better understand important topics related to health, wellness, and everyday living.


Please also review AIHCP’s Holistic Nursing Certification program and Nurse Courses see if it meets your academic and professional goals.  These programs are online and independent study and open to qualified professionals seeking a four year certification

A Guide to the Safe Management of Medical Waste in Healthcare Facilities

Medical waste disposal managementWritten by Rose Cartwright,

Correct handling of medical waste is everyone’s job, with the ultimate goal of protecting everyone, from medical, administrative, and custodial staff to patients, visitors, and the community at large. Improper waste management in a medical organization is a massive risk with far-reaching implications for both the facility and those who operate within it. Consider something as simple as an incorrectly stored sharp: If a staff member incurs a needlestick injury as a result of negligence, this creates another patient with another complex set of needs. It also triggers an administrative process involving internal reporting, the involvement of workers’ compensation, and, if the injury is serious enough, possible legal action.

The first step in avoiding this unpleasant chain of events is hiring a qualified medical waste disposal company. A credible waste disposal company will review your facility’s waste output and ensure that your containers and bins are appropriately suited for it, eliminating the chances of misplaced sharps or overflowing containers.

Understanding Medical Waste Classifications

Regulated medical waste typically falls into one of three categories:

Healthcare waste:

  • Pathological waste
  • Blood-contaminated items, such as bandages
  • Laboratory and treatment materials, such as body tissue

Sharps:

  • Needles
  • Lancets
  • Scalpels
  • Both broken and intact contaminated glass, such as drug vials

Pharmaceuticals:

  • Expired and unused medication
  • Disinfectants
  • Lab reagents

No matter what the waste item is, the moment it’s generated, it must be classified correctly and enter the requisite waste stream for its category. This includes general nonhazardous waste as well, which must have its own dedicated waste stream so as not to create confusion or add additional weight to regulated waste bins. For maximum efficiency and safety, this means the correct containers must be placed in the correct locations, with labels and easy-to-follow instructions for disposal.

Understanding the Regulations

It’s one thing to comply with federal, state, and local regulations in principle; it’s another to demonstrate that compliance in a legal setting. In order to meet legal compliance requirements, a facility must obtain and keep track of training records, inspection documentation, incident reports, vendor information, and corrective action paperwork. These documents must also be completed to code and signed off on by the necessary parties. Compliance officers rely on the written record in addition to the practical examination of the facility, and incomplete paperwork can delay rulings or create mistrust even if everything is above board.

Don’t be fooled by generic national waste management checklists, they may seem helpful, but healthcare settings call for a more robust set of standards than a general checklist can provide. OSHA’s Bloodborne Pathogens standard must be consulted in cases of exposure to infectious materials, post-exposure protocols, and handling sharps. If any of the medical waste produced is classified as hazardous, then EPA requirements also come into play. Transportation is also regulated, and although it may vary by jurisdiction, it must often comply with DOT requirements.

Segregation and Containment

Medical organizations are hectic and busy by nature, but this is no excuse for ignoring or rushing through waste segregation. There is no reason for a waste item to remain in a work area outside of its container for any reasonable length of time, and any instance of this immediately puts the facility at risk. Every staff member should be properly trained on the four categories of waste they will encounter at the facility: healthcare waste, sharps, pharmaceuticals, and general waste, as well as how to handle and segregate waste the moment it’s produced.

Set the staff up for success by placing sharps containers where they’re needed, with a visible fill line and instructions, as well as regular monitoring of both rigid containers and bags for every type of waste. Safety officers must also watch out for unlabeled receptacles, containers moved to undesignated spots for convenience, loose items beside bins, or patterns of staff choosing the nearest container instead of the correct one.

Safe Handling and Storage

Restrictive signage expressly forbidding anyone but authorized staff from entering waste-storage areas is the first line of defense against hazardous exposure following disposal. The second is appropriate personal protective equipment (PPE) for the staff that is permitted to collect, transport, store, or clean around medical waste receptacles. Policy should ensure the layout allows staff to clean between waste-area surfaces and prevents cross-contamination between different waste streams. Supervisors must verify these details during routine inspections. Spill kits, emergency contacts, and instructions should be easily accessible to staff at all times.

When a problem arises, there must be a clear chain of command in place, and staff members must understand at what point they are to stop work and escalate it to a supervisor or another employee. Finally, training should not only include this information, but also provide an explanation for the why; otherwise, the process may feel arbitrary and lead to less retention and application.

Treatment and Disposal

Compliance doesn’t end when waste leaves the premises, and since waste treatment is outsourced, facilities must verify where the waste is going and what type of treatment it will undergo or face further penalties. Incineration is appropriate for certain materials, but it also produces emissions and requires specific permits. Autoclaving uses steam sterilization and therefore reduces microbial contamination but is not suitable for pathological or chemotherapy waste, nor can it be used on anything that can melt and emit fumes. Chemical treatment and microwave systems are also useful in specific settings, but all these methods must be compliant and produce clear documentation trails in order to be approved. Medical organizations should work with service providers that employ compliant processes, hold the necessary permits, and have contingency plans in place.

Working With a Medical Waste Disposal Company

Selecting a suitable medical waste disposal provider involves verifying that every step of the process will be documented, including waste collection, any required treatment, and final disposal. A reputable provider will take the time to explain its permits, treatments, transportation, staff training, documentation practices, and plans for service disruptions, and won’t balk at questions posed by the facility during the initial consultation.

The final decision on pickup frequency and waste container type should be a collaboration between the provider and the facility, with changes in waste volume, emergencies, or operational changes being part of an ongoing dialogue. Healthcare organizations should also look into the waste company’s references and performance data to see how they perform, since a contract will not reveal this information. If accountability seems vague, transportation is unreliable, or documentation is incomplete, it is best to continue looking for another waste removal company, even if their prices are competitive. Low prices are not a guarantee of good service, and when a company’s prices seem “too good to be true,” they often are.

Staff Training

A facility’s waste disposal system touches every part of an organization and therefore must be part of training for every type of staff member. Because waste management is so crucial to the environmental health of the building, every department must work together to ensure compliance and avoid small mistakes that can snowball into habit. Team members should feel comfortable reporting when waste isn’t handled appropriately, a container is damaged, or a pickup is missed, not feel guilty or uncomfortable. To facilitate this, team leaders should foster a strong safety culture by making reporting easy and low pressure. It’s imperative that supervisors respond with understanding rather than from a place of blame, investigate what conditions led to the event, and communicate the next steps to the appropriate parties with clarity. Reporting that leads to practical changes that can be seen every day results in staff that is more likely to participate in prevention.

Training new hires begins with online modules that cover every facet of the waste disposal process and the duties specific to their position, but competency checks are what keep whole teams sharp and able to apply these concepts to real-world scenarios.

Documentation and Inspections

The best way to prepare for an outside audit is to perform internal ones routinely, with a focus on the design of the overall on-site waste handling system. The workload, equipment, and communication systems should also be evaluated, and observable issues should lead to practical, ongoing improvements. These improvements should be monitored for efficacy and updated or implemented in other locations based on the data. Key points of focus should be examining work areas, storage of waste, staff training, vendor documentation, and the consequences of earlier findings.

By tracking waste volumes by type, pickup frequency, container use, incidents, and exceptions, a facility can catch a compliance issue before an inspector does. For example, if regulated waste volume suddenly increases, it may mean medical waste was mixed in at some point, or if containers are consistently overflowing, pickups are likely scheduled at the wrong frequency. Routinely reviewing these types of patterns helps management take concrete action in advance of an inspection that could result in costly fines and reputational loss. Documenting whether any corrective actions changed the process for the better is also helpful when applying for funding to make further improvements down the line.

Balancing Cost and Safety

Cost and safety often go hand in hand, but both can be compromised when an organization takes shortcuts in an attempt to save money. Consider a facility that puts an overflow of medical waste into the general waste stream. Not only are they compromising the safety of countless people down the line, but they’re likely increasing their general waste cost, poisoning their own data for future audits, and risking fines that would far exceed the cost of a proper disposal service. Not to mention potential lawsuits from needlestick injuries.

Rather than guessing at where to cut corners, medical organizations should instead record waste volumes, service types and frequencies, and incident reports so they can get a clear picture of where financial losses are occurring. Improper waste handling is more often a cause than it is a solution, and the documentation will likely reveal that fact.

Proper container selection, vendors that consolidate services, properly segregated waste, and contracts with providers that reflect actual patterns of waste generation are genuine improvements that may end up paying for themselves. It may be tempting to invest in the latest technology for training and maintenance, but management must assess whether the investment is likely to produce a return or is just serving to keep up the appearance of progress.

Small Steps Forward

Small tangible adjustments to behavior and equipment create greater lasting change than sweeping overhauls. Simplifying where waste receptacles are placed, removing improper containers, making the labels clear, conducting regular observations, and observing incident trends to inform retraining efforts all lead to gradual improvement over time. These improvements should all go hand in hand with relevant training for the appropriate staff, tailored to each individual’s position. Management should also continually reassess vendor relationships to ensure that their contracts are still followed and ongoing performance is up to par.

Waste volume increasing while storage and pickup schedules remain unchanged, and improper segregation of waste are larger issues that must be addressed before the situation goes on unnoticed for weeks, creating a genuine hazard. Sending regulated waste into general waste streams poses a risk to both human and environmental health, so keeping it separated is paramount.

A Complete System

Waste management is no less important than other operational functions and must be treated as such by medical organizations. Beginning with clear expectations will set the staff up for success and ensure every team member understands their role in waste-handling safety. When services expand, contract, or become modified in any way, procedures should be reviewed again to eliminate gaps in comprehension.

A successful waste management program connects infection prevention, environmental safeguards, and general facilities management to create a system that keeps people safe and quotas met.


Author Bio:

Rose Cartwright is an author and blogger whose work explores recycling, sustainability, and environmental science. When not writing, she can be found riding her horse, Chestnut, or facilitating creek cleanup initiatives in her hometown of Ithaca, New York.


Please also review AIHCP’s Managed Health Care Certification program and CE courses see if it meets your academic and professional goals.  These programs are online and independent study and open to qualified professionals seeking a four year certification

Can Preventive Care Be Too Fragmented to Work?

Discussion about treatment results

Written by Ryan Harris,

You can do everything you’re supposed to do and still not know whether anyone has looked at the whole picture.

They had the physical. They got the bloodwork. Maybe they saw a cardiologist, scheduled the mammogram, had a skin check, and finally followed through on that referral from last year. Ask what all those appointments added up to, though, and the answer may be harder to find.

The trouble usually isn’t a complete lack of care. It’s that the care happened in pieces. Different offices saw different parts of the story, at different times, in different systems.

That can leave a patient with plenty of medical activity but no obvious plan.

When separate appointments stop adding up

Specialists are part of good care. The problem is that each specialist is working from a narrower part of the record, while primary care may not have every result in front of them.

Sometimes the patient ends up filling the gaps, repeating the history at each visit and trying to remember which office has which result.

Picture a fairly common sequence. A primary care doctor notices something in routine bloodwork and recommends additional testing. The test is performed at an outside facility. A specialist reviews one part of it three weeks later. Another result lands in a patient portal without much context. By the next primary care visit, several people may have touched the case, but the information can still be sitting in separate records.

For someone who has trouble fitting several appointments into a workweek, a comprehensive executive physical can put imaging, lab work, physical testing, and physician review into a single visit. The useful part isn’t simply doing more tests in less time. It’s having the results considered together rather than arriving as disconnected pieces over several months.

AHRQ has documented how communication problems in outpatient care can create safety issues. Its work on patient safety in ambulatory care covers practical risks around referrals, medication information, test results, and follow-up when several people are involved in the same patient’s care.

AIHCP’s overview of the health care delivery system also shows how many parts sit behind a single visit. Records, referrals, facilities, payment, and follow-up all have to connect well enough for the next clinician to know what has already happened.

The problems are often small enough that they don’t look important at first. A medication list is outdated in one chart. A specialist asks for a scan the patient assumed had already been sent. Two doctors order similar blood tests because neither can see the other’s recent results. A referral is placed, but no appointment is ever made.

One missed handoff probably won’t unravel a person’s preventive care. Several of them can.

More testing can create its own kind of confusion

One response to fragmented care is to order more tests, hoping a larger set of results will provide a clearer answer.

More testing can help in the right situation, but it can also leave the patient with a larger pile of results that still need interpretation.

Screening also depends heavily on the person being screened. The U.S. Preventive Services Task Force changes recommendations based on age, sex, smoking history, pregnancy status, and other risk factors, so the same test may be appropriate for one patient and unnecessary for another.

Consider two 48-year-olds. One has a family history of early heart disease, rising blood pressure, and metabolic markers that have been moving in the wrong direction. The other has none of those issues but is overdue for routine cancer screening. Giving both the same giant checklist of tests may look thorough, but it doesn’t necessarily make either person’s care more thoughtful.

The reverse happens too. Someone gets a basic lab panel, sees mostly normal numbers, and takes that as evidence that everything important has been covered. An age-appropriate screening may still be overdue, or a follow-up recommended last year may never have been scheduled.

A test has limited value if nobody reviews what it changes about the patient’s care.

One result rarely settles the question by itself. A mildly abnormal number that has been stable for years may be less concerning than a result still inside the reference range but moving quickly. Medications, symptoms, family history, weight changes, earlier imaging, and new diagnoses all affect how a clinician interprets the number.

That is easier to judge when the clinician can see the previous results and the surrounding history instead of opening one portal at a time.

Otherwise, the patient may leave with a long list of results but no clear sense of what needs attention.

The six-month follow-up is often more important than the February physical

Say a patient has a routine physical in February and their cholesterol is higher than it was last year. The doctor suggests a few changes and asks for another lab test in six months.

Life moves on.

In April, the patient goes to urgent care for something unrelated. In June, a cardiologist gets involved because of family history. August comes around, but the repeat test isn’t on anyone’s calendar. The patient assumes the cardiologist is watching the issue. The cardiologist thought primary care was handling it. Primary care is waiting for the patient to schedule the lab.

There was no dramatic failure. Nobody ignored an emergency. A fairly ordinary follow-up simply fell into the space between offices.

By itself, that missed repeat test may not seem serious, but it means the original plan was never completed.

AHRQ defines care coordination around organizing care and sharing information among the people involved. In practice, that can be as basic as checking whether a referral happened, reading the specialist’s note, confirming repeat labs were completed, and deciding which clinician is responsible for follow-up.

AIHCP’s discussion of case management and utilization review deals with similar questions from a professional perspective. Completing the appointment is only part of the job. Someone still needs to check what came out of it, whether another step is due, and who is meant to handle it.

Patients feel the difference immediately.

“Your labs look mostly fine” isn’t much of a plan.

“Your blood pressure looks good, your cholesterol needs another check in September, and you’re still due for the screening we discussed last year” is something a person can act on.

The second conversation doesn’t require more technology or a more expensive test. It requires someone to keep track of the unfinished business.

Patients shouldn’t have to coordinate everything themselves

Being an engaged patient helps. In practice, that may mean carrying an updated medication list, knowing the important parts of your family history, keeping major reports handy, and asking what needs to happen after the visit.

But patients shouldn’t have to chase every record, referral, and result themselves just to keep the process moving.

With several clinicians involved, the administrative work adds up quickly. One portal holds the lab work. One office asks for the actual scan instead of the written report. Another needs the name and dose of a prescription from a different system. A referral may also sit in limbo until the patient notices that no one ever called.

Most people are managing this on top of work and family. A nonurgent lab or referral can disappear from the to-do list for months.

That is often how a six-month follow-up turns into a twelve-month one.

Better coordination doesn’t depend on every provider using the same software. Smaller workflow choices can close plenty of gaps. Schedule repeat testing before the patient leaves. Confirm that an outside report reached the chart. Before ordering a repeat test, check the recent record first. If a specialist is involved, the patient should also know whether that office or primary care is supposed to follow the result.

The last minute of the visit matters more than it sounds. “Come back if anything changes” doesn’t tell a patient whether anyone is expecting a repeat test, a call, or a return appointment. “Repeat this in six months, and our office will review the result with you” gives them a date, an action, and a clear owner.

AIHCP’s discussion of healthcare resource management is relevant here because wasted resources are not limited to budgets or staffing. Repeated tests, missing reports, and avoidable calls also use clinician time and patient time without necessarily improving care.

Care will still be spread across different places. A primary care office may use an outside lab, a hospital may handle imaging, and a specialist may keep a separate record. The practical question is whether the next clinician can see enough of that history to avoid starting over.

The patient shouldn’t have to rebuild that history from memory at every appointment.

Wrap-up takeaway

Preventive care starts to lose value when each appointment is treated as a separate event. Sometimes the test was done, but the result never made it back to the clinician who was supposed to act on it. Follow-up deserves as much attention as the screening itself. Patients can help by keeping copies of important reports and asking who is responsible for the next step, but the system still needs to do its share of the tracking. If several doctors are involved, it should be clear which office is watching each unresolved issue. Today, pull up your last physical or specialist note and check whether any repeat lab, referral, or screening was recommended without a date or a named person responsible for following it.

Author’s Bio

Ryan Harris writes about preventive health, longevity, and the changing role of diagnostics in modern healthcare. His work looks at how earlier risk detection, better health data, and more comprehensive assessments can help people make more informed decisions about their long-term health.


When the Hospital Is Hundreds of Miles Away: The Complexities of Medical Transport 

Speeding ambulanceWritten by Marchelle Abrahams,

The search for a missing air ambulance drew widespread news coverage over the weekend. A medical crew was reportedly transporting a patient and a family member from Bermuda to Boston when the plane went missing off the coast of Nantucket Island.

The unfortunate incident has left many questions unanswered, including how an aircraft could disappear moments after losing contact with air traffic control. 

And the 800-pound gorilla that hospital case managers are wondering about: transporting patients is a complicated web of safety and protocol. Where were the weak spots?

Answers remain vague, but that doesn’t discount the fact that medical transportation is a complex system that becomes even more intricate when the hospital is states away.


The Growing Need for Medical Transport

An aging population, rising rates of chronic illness, and a push to reduce missed medical appointments are part of the demand.

They’re also why the U.S. non-emergency medical transportation (NEMT) market is expected to grow to $13.43 billion by 2031, according to Research and Markets data.

NEMT providers serve Medicaid beneficiaries and patients in need of transportation to medical facilities for regular appointments and check-ups. Ambulance services, wheelchair assistance, stretcher services, flight services, and courier services are included.

However, working in healthcare gives us a bird’s-eye view of the challenges. Hospital case managers are probably the ones to witness this firsthand.

Inflation and operating costs leave many providers feeling squeezed, particularly in rural regions. The industry continues to face hurdles related to administrative complexity, broker dependencies, and compliance.

But we’re seeing some improvement. Strategy & Stats reports that collaborations among hospitals, private air medical transport companies, and insurers are improving coordination of patient transfer services and increasing access to air transportation services.


When Specialist Care Crosses State Lines 

Interstate medical transportation isn’t as cut-and-dry as transporting a patient and being done with it. Well, that’s what the general public thinks.

When it comes to medical transportation between states, providers must navigate a patchwork of federal rules, insurance policies, and operational scopes. There’s no single universal long-distance law dealing with interstate patient transport.

Hospital case managers and discharge planners usually handle the logistics of long-distance hospital transport. Discharge planning alone requires mountains of admin work. ACC Medlink suggests enlisting a professional, reliable transport partner that can provide documentation support.


The Role of Case Managers in Patient Transfers 

Nurse case managers are the unsung busy bees working behind the scenes. You ensure a patient’s transfer is safe, smooth, and continuous across care settings.

You evaluate the patient’s physical status, monitor vital signs, and decide whether the patient is stable enough for movement.

Probably your most underestimated role is advocating for your patient. You explain the inner workings of transferring them from one hospital to another facility and provide a vital link between them and their care team.

“During the 1960s and in subsequent decades, a growing patient rights movement embraced the importance of informed consent for honoring patients’ autonomy. Patient advocates arose as an important voice in this movement by educating patients about their rights and helping them participate more fully in decisions about their healthcare.” – Jennifer Schlinger, Clinical Associate Professor of Social Work, via The Conversation.


Access Barriers

Delayed care will remain a moot point as long as access to medical transport is only reserved for those who can afford it.

A 2024 review published in the Journal of Transport & Health paints a multifaceted picture. People in rural communities have to travel long distances to access healthcare services. The link between distance and/or travel time and healthcare service access hasn’t always been clear. 

The research looked at how distance and travel time affect access to healthcare for people living in rural and remote areas of developed countries. It found that travel time may be a better measure of healthcare access than distance, particularly for people living outside major cities.


FAQs

What is medical transportation between states?

Medical transportation between states refers to moving a patient across state lines to access healthcare. Depending on the patient’s condition, this can involve ground ambulances, non-emergency medical transportation, wheelchair or stretcher services, or medical flights.

Who arranges interstate medical transportation?

Hospital case managers, discharge planners, and healthcare teams often coordinate patient transfers. They may need to assess the patient’s medical needs, communicate with the receiving facility, arrange transportation, and ensure the necessary documentation is in place.

Why might a patient need to travel to another state for medical care?

Patients may need to cross state lines when specialized treatment is unavailable locally. This can include specialist consultations, advanced procedures, rehabilitation, transplant services, or treatment at a facility with specific expertise.

Is medical transportation between states covered by insurance?

Interstate medical transportation coverage depends on the patient’s insurance plan, medical needs, and the type of transportation required. Medicaid and private insurers may have specific eligibility and authorization requirements, so patients and care teams should confirm coverage before arranging transportation.


Medical Transportation: Key Stats 

Stat What it Tells Us
$13.43 billion Projected value of the U.S. non-emergency medical transportation market by 2031 
Travel time vs. distance Research suggests travel time may provide a better picture of healthcare access than distance alone
Cross-state transfers Interstate transfers can involve coordination between hospitals, insurers, transport providers, and healthcare professionals
Multiple transport options NEMT can include ambulances, wheelchair transport, stretcher services, medical flights, and courier services


Getting Patients There Is Part of the Care 

Healthcare doesn’t end when a patient leaves one hospital. Transporting them to the next facility is just as important. We may not know what happened on that fateful air ambulance flight.

But we do know it doesn’t define the NEMT industry. Yes, challenges remain top of mind, yet every case manager’s goal is to get patients from point A to point B with as few complications as possible.

Author bio

Writer by day, dream catcher by night. Marchelle Abrahams cut her teeth in the infancy of the internet when the dial-up sound of the modem was more than a soundbite at a rave. Not a Millennial and not a Boomer, Marchelle is an in-betweener, making her a special breed of human. As a qualified journalist, Marchelle believes her superpower is stringing a few words together and people reading them.


References:

Search suspended for missing Ontario-based air ambulance with four Canadians aboard : U.S. Coast Guard. (2026, October 5). Nationalpost. https://nationalpost.com/news/four-canadians-aboard-ontario-based-air-ambulance-missing-off-u-s-coast 

Ltd, R. a. M. (n.d.). US Non-Emergency Medical Transportation Market Size & Trends. Research and Markets Ltd 2026. https://www.researchandmarkets.com/report/united-states-non-emergency-medical-transportation-market 

Kardani, P. (2026, October 7). U.S. air ambulance services industry: emergency care insights. SNS Insider. https://www.snsinsider.com/blogs/air-ambulance-services-industry 

Schlinger, J. (n.d.). What is a professional patient advocate, and why might you need one? The Conversation. https://theconversation.com/what-is-a-professional-patient-advocate-and-why-might-you-need-one-281971 

Impact of distance and/or travel time on healthcare service access in rural and remote areas: A scoping review. Journal of Transport & Health July 2024. https://www.sciencedirect.com/science/article/pii/S2214140524000653 

Us, J. K. W. (2026, October 5). A surgeon shortage creates challenges in rural communities. The Week US. https://theweek.com/health/a-surgeon-shortage-creates-challenges-in-rural-communities 

Please also review AIHCP’s Case Management Certification program and our CE courses as well, to see if they meet your academic and professional goals.  These programs are online and independent study and open to qualified professionals seeking a four year certification

Reduction, Not Only Abstinence: Meeting Patients in the “Gray Area” of Alcohol Use

drunk man drinking alcohol at table at night. Acceptable or in the gray area of alcohol use?

Most people whose drinking exceeds healthy limits will never walk into an addiction clinic. They are not dependent on alcohol, and they do not meet the criteria for a severe use disorder. Many are not looking for treatment at all. Their drinking is still not harmless, and a growing number of them know it. They sit in what clinicians and patients alike describe as a gray area: too much to ignore, not enough to resemble the treatment system as most people picture it.

The clinical term of art for this group is “unhealthy alcohol use.” The U.S. Preventive Services Task Force (USPSTF) defines it as a spectrum of behaviors that runs from risky drinking to alcohol use disorder. Risky or hazardous drinking means drinking above recommended limits, in a pattern that raises the risk of health consequences without meeting the criteria for an alcohol use disorder. An alcohol use disorder is a different matter: a medical condition in which a person struggles to stop or control drinking despite the consequences, and it can be mild, moderate, or severe.

The distinction shapes how care is organized. A person who drinks above the limits but has no disorder is unlikely to accept, or need, an abstinence-only pathway. A person with a severe disorder needs much more than a brief conversation. Between those poles lies a large, quiet group that the health system mostly misses.

Why this group is easy to miss

People who drink in the gray area rarely describe themselves as having a problem. Popular culture still draws a hard line between “alcoholics” and everyone else, and that framing can work against early change: when cutting back reads as an admission of a problem, reluctance to try tends to grow. Research documents a second barrier. A scoping review led by clinical psychologist Devin Banks found that Black people in substance use treatment feared being judged by employers, police, and others, and that this stigma can be a barrier to treatment.

Drinking to cope is also normalized. About two-thirds of adults in the United States report drinking in the past year, and nearly a quarter report binge drinking in the past month. When a drink is how someone marks the end of a workday, cutting back is less a medical decision than a social and personal one.

The scale of the harm justifies attention. Excessive alcohol use is one of the most common causes of premature death in the United States; the Task Force cites an estimated 88,000 alcohol-attributable deaths a year from 2006 to 2010, from acute causes such as injuries and from chronic conditions such as liver disease.

What the evidence supports

Screening for unhealthy alcohol use in primary care, followed by brief behavioral counseling for patients who screen positive, carries the Task Force’s Grade B recommendation for adults 18 and older, including pregnant women. The Task Force concluded with moderate certainty that the net benefit is moderate. For adolescents aged 12 to 17, the evidence remains insufficient to weigh benefits against harms.

The benefit is real but not dramatic, and the numbers are worth knowing. Pooled trial results behind the recommendation show that brief counseling reduced the odds that a patient would exceed recommended drinking limits by roughly 40 percent (odds ratio 0.60; 95% CI, 0.53 to 0.67), and lowered the odds of a heavy-use episode by about a third, with outcomes measured at 6 to 12 months. The Task Force also bounded the harms of screening and brief counseling as small to none.

Two details keep the picture honest. The interventions that worked varied in their components, administration, length, and number of interactions, and the Task Force could not identify which characteristics were clearly associated with better outcomes; the conversation matters more than any fixed script. Part of the case for reduction also rests on indirect evidence: epidemiologic studies link reductions in drinking with lower risks of illness and death, even though they cannot show that a brief conversation produced the change on its own.

External assessments point in the same direction. The World Health Organization (WHO) has concluded that no level of alcohol consumption is safe for health, that alcohol causes at least seven types of cancer, and that risks start from the first drop of any alcoholic drink; as one WHO official puts it, the less you drink, the safer it is. A reduction-focused conversation does not have to settle debates about safe levels. It only has to help someone move in the safer direction.

The service model that carries this into practice is SBIRT: screening, brief intervention, and referral to treatment. The Substance Abuse and Mental Health Services Administration (SAMHSA) describes SBIRT as a public health approach to delivering early intervention and treatment services in primary care centers, hospital emergency rooms, trauma centers, and other community settings: a quick screen assesses the severity of use, a brief intervention builds insight and motivation toward change, and a referral pathway connects people who need more to specialty care.

What this looks like in practice

Whatever your role, you are better positioned than you may think. Nurses notice patterns at intake. Case managers hear how the week actually went. Chaplains and counselors sit with the stress that drinking is often managing. None of these roles requires prescribing authority, and none requires a full clinical assessment to be useful.

Screening can be short. One- to three-item instruments such as the AUDIT-C and the single alcohol screening question have the best accuracy for detecting unhealthy alcohol use in adults, and the AUDIT-C takes a minute or two to administer.

When someone screens positive, the brief intervention is a conversation rather than a lecture. In SAMHSA’s description, it works by increasing a person’s insight and awareness about their substance use and their motivation toward change. Cutting back and stopping altogether are both defensible goals; the evidence behind reduction-focused care is what makes it reasonable to support someone who is not ready to quit. People can take smaller steps toward health even when they are not ready for permanent abstinence. For patients who want structured support between visits, patient-facing programs such as Sunnyside offer app-based tracking, coaching, and clinician-supervised options for those who want to reduce. Programs like this work alongside clinical care, not in place of it, and they are one option among many a patient can weigh.

Language does quiet work here. “Alcoholic” remains a stigmatizing term, and the sober curiosity framing works partly by setting the label aside: anyone can try cutting back, without having to define themselves as a problem drinker first. And when a cutback attempt fails, that failure is information: practitioners in this space treat it as a signal that a plan, a goal, or a support level needs adjusting, not as proof that the person cannot change.

When moderation is not the right goal

Reduction-focused care has a safety boundary, and it is not optional. Moderation is not an appropriate goal for someone with a physical dependence on alcohol. Withdrawal in that situation can be fatal, and patients who become nauseated, shaky, or otherwise unwell when they try to cut back need supervised medical withdrawal rather than a self-guided plan. Some of those patients might be better off seeking permanent abstinence, and others need formal treatment; the treatment navigator listed below exists for that handoff. The screening recommendation itself is written for people who are not already in evaluation or treatment for alcohol problems.

Pregnancy is its own case: alcohol use during pregnancy is one of the major preventable causes of birth defects and developmental disabilities, and brief counseling increased the likelihood that women remained abstinent from alcohol during pregnancy.

The takeaway for practice

The next step for any role in this work is a small one. Screen when you can, and let the screening become a conversation about goals rather than a verdict about drinking. Treat reduction as a legitimate goal for patients who are not ready for abstinence, and keep the safety boundary in view: withdrawal risk and pregnancy belong with clinicians, and a timely handoff is part of the care. That is the practice in its everyday form: a question, a conversation, a goal the patient chooses, and a clear line where clinical care takes over.

Resources to share with patients and clients

Two free NIAAA resources are worth knowing by name. Rethinking Drinking offers practical tools for adults who want to examine or cut back on their drinking, including strategies for cutting down and a free booklet. The NIAAA Alcohol Treatment Navigator is aimed at people who may need treatment for an alcohol use disorder; it focuses on evidence-based care, includes questions to ask a potential provider, and carries no commercial sponsorship.


Author’s Bio:

This article is brought to you by the expert content team at nexuse backlinks agency, specializing in digital marketing, SEO, and quality online resources


Please also review AIHCP’s Substance Abuse Practitioner Program and  CE courses to see if it meets your academic and professional goals.

Where Patient Data Goes After the Handoff: The Hidden HIPAA Risk in Care Coordination

Medicine insurance security care for life. Hospital diagnosis design, health care document filling concept. Document health diagnoses medical insurance. Text and cartoon character vector illustration

Written by Ryan Harris,

A patient can leave the hospital with new prescriptions, follow-up visits, and home care already being arranged. Before they’ve even settled back in at home, parts of their medical record may have been sent to several different providers and systems.

That kind of movement is routine in healthcare. Care often depends on people in different offices and organizations being able to share information without slowing things down.

The trouble starts when everyone knows where the information came from, but nobody is quite sure where all the copies went. A discharge summary becomes an attachment. The attachment gets downloaded. Someone uploads it into another portal. A case manager keeps a working copy because the referral isn’t finished yet. None of those actions looks especially risky on its own.

Put them together, though, and the patient record is suddenly much harder to follow.

A secure handoff doesn’t settle what happens next

Case managers deal with this constantly. Their job often involves getting the right information to the right person before a delay turns into a bigger problem. The role of a case manager can involve coordinating providers, reviewing care plans, handling referrals, speaking with insurers, and helping patients move between settings. That work produces a lot of legitimate data sharing.

Picture a fairly ordinary discharge. A hospital sends a summary to a rehabilitation facility through an approved system. The facility downloads the document, adds it to its own chart, and forwards part of the information to a pharmacy. Meanwhile, a case manager uploads supporting records to an insurer for authorization.

The first transfer may have been handled exactly as intended. That still leaves a long list of practical questions. Where is the downloaded copy now? Does the rehabilitation facility back up that folder automatically? Who can open it? Does the insurer’s portal keep attachments after the authorization closes? Is someone maintaining another copy while waiting for a response?

Organizations that rely on external infrastructure to store or process ePHI also need to know how their HIPAA-compliant cloud services handle access, backups, recovery, and the systems underneath the application staff actually see. Those details matter long after somebody clicks “send.”

The HIPAA Security Rule is concerned with electronic protected health information that is created, received, maintained, or transmitted. “Maintained” is easy to overlook. A record doesn’t stop being sensitive because nobody is actively using it today.

Healthcare workers usually notice the visible handoff. They remember the fax, portal message, referral, or phone call. The less visible part is what happens afterward, when the information settles into somebody else’s workflow.

One patient record can become six working copies

Most healthcare organizations don’t have one neat version of a patient record moving from place to place.

They have an official record and a collection of working copies around it.

A nurse may export a medication list before calling another provider. A case manager might keep a spreadsheet showing which referrals are still pending. A utilization review team may attach clinical notes to an authorization request. A home health agency could download a PDF because the referring hospital and its own software don’t communicate cleanly.

There’s nothing unusual about that. In fact, some of these steps are what keep care moving.

But copies tend to outlive the reason they were created.

The spreadsheet that was meant to last three days is still on a shared drive four months later. A former employee still has access to a referral portal because that account wasn’t tied into the normal offboarding process. A desktop folder contains discharge paperwork that was supposed to be temporary. None of these situations requires a sophisticated attack. They exist because healthcare work is busy, systems don’t always cooperate, and temporary fixes have a habit of becoming permanent.

That’s where privacy controls can look stronger on paper than they do in practice.

An organization can lock down its EHR pretty well and still have patient information drifting through smaller systems that get far less scrutiny. AIHCP’s discussion of patient confidentiality challenges touches on access controls and secure communication, but those safeguards only help if you know everywhere the information is ending up.

A better way to spot problems is to look at what actually happens during a discharge. A file might be downloaded for review, uploaded again to a referral portal, mentioned in an email, and copied into a tracking sheet while staff wait for a response. If that referral drags on for several days, those extra copies can easily stick around longer than anyone intended.

You’ll often learn more from that conversation than from a polished diagram of the organization’s approved systems.

Vendors make the trail harder to see

Healthcare organizations depend on outside companies for all kinds of ordinary functions. Billing, scheduling, cloud storage, transcription, analytics, messaging, document management, and case management software may all involve outside vendors.

Staff rarely see the full stack behind those services.

Suppose a behavioral health practice uses an online case management system. The practice deals with one company and sees one login screen. Behind that screen, the application may rely on another provider for infrastructure, another for backups, and another for automated communications.

That doesn’t mean anything improper is happening. It does mean the data trail is longer than the user interface suggests.

HHS guidance on business associates addresses situations where outside organizations perform functions involving protected health information. Subcontractors can also become part of those relationships. For the healthcare organization using the service, the practical concern is understanding who can touch the data and under what arrangement.

“We use a HIPAA-compliant vendor” isn’t a very revealing answer.

A better review gets specific. What information is the vendor receiving? Is it keeping the data or merely passing it through? Can vendor employees access production systems? Who controls backups? What happens to stored information when the contract ends? Does the service depend on additional companies that also handle ePHI?

The answers don’t all need to come from nurses or case managers. Most won’t. But frontline staff can identify something the legal and IT teams can’t always see from contracts: how the service is actually being used.

That matters because the official use and the real use aren’t always identical.

A system purchased for referrals may become a place where staff also upload discharge records. A shared portal intended for one department may slowly become useful to three others. A vendor can end up handling more patient information than anyone anticipated when the agreement was signed.

NIST’s guidance for implementing the HIPAA Security Rule places heavy emphasis on understanding risk rather than simply collecting controls. That distinction is important. You can’t judge the risk around a vendor very well if nobody knows what information staff are actually putting into the system.

The workaround is often telling you something

Some of the most revealing privacy conversations start with a sentence nobody wants to hear:

“I know we’re not supposed to do it this way, but…”

Maybe the referral portal goes down regularly, so employees found another way to send paperwork. Maybe the case management system doesn’t show everything staff need on one screen, so someone created a separate spreadsheet. Maybe clinicians take screenshots because two systems make it painfully difficult to compare information.

It’s easy to treat those situations as training failures.

Sometimes they are. Sometimes they’re workflow failures.

If ten employees keep doing the same workaround, there’s probably a reason. Telling them for the eleventh time that the approved process is the approved process may not change much if the approved process prevents them from getting a patient discharged before the end of the day.

That doesn’t mean unsafe shortcuts should be accepted. It means they’re worth investigating rather than merely policing.

AIHCP has already looked at HIPAA compliance in a digital healthcare environment, including issues involving cloud storage, portals, mobile technology, and outside vendors. Care coordination is where many of those systems collide. A patient’s information can move through several of them during a single episode of care.

Wrap-up takeaway

Most people involved in a patient’s care are trying to do the same thing: get the information where it needs to go without slowing care down. The problem is that every extra download, portal, vendor, and temporary file leaves another place to keep track of. Over time, those small decisions can create a data trail that nobody fully owns anymore. That’s worth paying attention to because the weak spot may not be the main system everyone watches closely. It may be the forgotten account or working file sitting just outside it. 

Author Bio:

Ryan Harris is a writer covering technology, workplace learning, and operational risk. He writes about how training, digital systems, and everyday workflows affect safety, privacy, and decision-making, with a focus on making complex professional topics clear and practical.


Please also review AIHCP’s Managed Health Care Certification program and CE courses see if it meets your academic and professional goals.  These programs are online and independent study and open to qualified professionals seeking a four year certification

Peptides and Exercise Recovery: What Current Research Can and Cannot Tell Us

Doctor, laptop and writing notes at night thinking about healthcare solution, idea or planning at hospital. Woman medical nurse working late in focus with notebook and computer for research at clinic.Written by Alex,

Recovery after strenuous resistance exercise or a soft-tissue injury is not a single event. It involves a sequence of overlapping biological processes. Mechanical loading can disrupt muscle proteins and connective tissue, alter local signaling, and trigger an inflammatory response. In the hours and days that follow, immune cells, fibroblasts, muscle cells, blood vessels, and components of the extracellular matrix participate in repair.

Muscle protein synthesis increases after resistance exercise, while injured tendons move through overlapping inflammatory, proliferative, and remodeling phases in which collagen is produced and reorganized. With repeated and appropriately dosed loading, these short-term responses contribute to longer-term tissue adaptation.

Peptides are frequently mentioned in discussions of this biology because the human body uses many peptide and protein signals to coordinate cellular activity. Hormones, growth factors, cytokines, and other signaling molecules can influence inflammation, vascular responses, protein turnover, and tissue remodeling. That observation is biologically relevant, but it does not establish that administering a separate peptide drug will accelerate recovery, heal an injury, or improve performance. Normal signaling inside the body and treatment with an externally administered compound are different scientific questions.

Why Peptides Are Not One Therapeutic Category

The word peptide describes a chemical structure a chain of amino acids not a uniform clinical effect. Different peptides act through different receptors and pathways, have different half-lives, and can produce very different effects depending on dose, tissue exposure, route of administration, and the health of the person receiving them.

Some peptide-based medicines have extensive clinical trial data and FDA-approved indications. Others remain investigational and have little reliable human evidence for the uses promoted online.

This distinction is especially relevant in exercise medicine. A plausible molecular mechanism is an early stage of research, not proof of a useful clinical outcome. A compound can alter angiogenesis, inflammatory mediators, fibroblast activity, or growth-factor signaling in a laboratory model without improving pain, physical function, return-to-activity time, reinjury risk, or long-term tissue integrity in people. Those outcomes require appropriately designed human studies.

BPC-157 Illustrates the Evidence Gap

BPC-157 is a 15-amino-acid peptide that has attracted attention for proposed effects on tendon, ligament, muscle, bone, and other tissues. Much of that interest originates from cell and animal experiments.

A 2025 systematic review of the orthopedic and sports-medicine literature identified 36 eligible studies, of which 35 were preclinical and only one was a clinical musculoskeletal study. That human report involved 12 patients receiving intra-articular treatment for chronic knee pain; seven reported relief lasting more than six months. The study was small and retrospective, however, and lacked the controlled design required to establish efficacy or characterize safety reliably.

A separate 2025 review reached a similar conclusion about the evidence gap. Although animal studies describe effects involving angiogenesis, fibroblast activity, inflammatory signaling, and tissue repair, the authors found only a very small number of human pilot studies across several unrelated clinical settings. Large, rigorous clinical trials capable of defining musculoskeletal benefits, adverse effects, appropriate dosing, and longer-term outcomes are lacking.

FDA materials provide another reason for caution when interpreting the available research. In 2026, the agency evaluated BPC-157 free base and BPC-157 acetate in connection with possible inclusion on the section 503A bulk drug substances list. FDA stated that neither form is a component of an FDA-approved drug and concluded that available clinical information was insufficient to characterize safety adequately.

Its review also discussed potential immunogenicity, peptide-related impurities, uncertainties surrounding active-ingredient characterization, and the lack of human data for several proposed routes of administration.

The FDA evaluation concerned a nominated use in ulcerative colitis rather than exercise recovery, so it should not be treated as a direct test of musculoskeletal effectiveness. It does demonstrate why questions about formulation, identity, human safety data, and regulatory status cannot be separated from clinical discussions of these compounds.

Why Animal Healing Data Cannot Be Assumed to Apply to Humans

Preclinical research is essential for identifying biological mechanisms and deciding which treatments deserve further investigation. Translation to clinical care, however, is not automatic.

An experimentally created tendon defect in a rodent is different from chronic human tendinopathy, a partial tear in a recreational athlete, or rehabilitation following surgical repair. Age, underlying health, injury severity, mechanical loading, and rehabilitation conditions can all alter recovery.

Dose is another major consideration. A quantity that produces a biological response in an animal cannot simply be converted into a human dose according to body weight. Absorption, metabolism, tissue distribution, clearance, and receptor activity can differ substantially between species. Route of administration also changes exposure: oral, subcutaneous, intravenous, intra-articular, nasal, and other routes cannot be assumed to produce equivalent effects or risks.

Study design adds further limitations. Animal experiments commonly use controlled injuries, relatively small samples, short observation periods, and laboratory endpoints such as histologic appearance, tensile strength, or expression of signaling molecules.

Clinical decision-making requires additional information. Patients and clinicians need to know whether treatment improves meaningful outcomes such as pain, mobility, function, return to activity, recurrence, and quality of life and whether adverse effects emerge after repeated or prolonged exposure. A favorable change in a microscopic marker does not by itself demonstrate better recovery for a patient.

When Patients Ask About Recovery Peptides

Patients increasingly arrive at appointments after encountering social-media discussions, clinic websites, commercial claims, and physician-authored or physician-reviewed resources such as peptide therapy guidance from Dr. Jonathan Snipes. A useful clinical response is to identify exactly what is being claimed and then place that information alongside the quality of the human evidence, available safety data, and the patient’s individual circumstances.

The first question is which compound the patient is actually considering. The specific chemical form, proposed dose, route of administration, and intended condition all matter. Clinicians can then ask whether evidence exists from controlled human studies for that particular indication or whether the rationale comes mainly from laboratory and animal experiments.

Regulatory status also deserves attention: an FDA-approved medication, an investigational substance, a compounded preparation, and a product purchased from an online supplier do not carry the same evidence or quality assurances.

Product quality is particularly relevant when the substance lacks an approved commercial drug formulation. Identity, purity, sterility, peptide-related impurities, storage conditions, and batch consistency can influence risk. FDA’s BPC-157 materials, for example, have noted concerns about characterization and inconsistent naming of related substances.

Medication history and medical conditions should also be reviewed rather than considering a recovery peptide in isolation. When human safety information is sparse, uncertainty extends to interactions, repeated exposure, immune reactions, and use in people with significant medical conditions. Injectable formulations raise additional questions about sterility and administration practices.

Just as important, the original musculoskeletal problem should be diagnosed. Persistent pain described as a tendon injury can arise from a partial tear, joint disease, referred pain, nerve involvement, stress injury, or another disorder requiring different management.

Beginning an experimental intervention without clarifying the diagnosis can complicate or delay appropriate imaging, rehabilitation, activity modification, or medical treatment.

Competitive athletes face an additional issue unrelated to whether a compound eventually proves medically useful. The 2026 World Anti-Doping Agency Prohibited List specifically names BPC-157 under S0, Non-Approved Substances, and prohibits it at all times, both in and out of competition. Athletes governed by anti-doping rules therefore need to consider eligibility and testing consequences independently of discussions about possible therapeutic effects.

Conclusion

Peptide science is biologically interesting because peptide and protein signals are part of the communication systems involved in inflammation, tissue repair, protein synthesis, vascular responses, and remodeling. Those physiological observations, however, do not establish the safety or effectiveness of administering a particular peptide as treatment.

Evidence must be evaluated compound by compound, for the specific indication and route being proposed. In the case of BPC-157, the preclinical musculoskeletal literature is substantially more developed than reliable human clinical evidence.

Exercise programming, adequate nutrition, accurate diagnosis of injuries, progressive rehabilitation, and appropriate medical care remain separate clinical considerations and should not be replaced by assumptions drawn from early peptide research.


Author BIO

Alex is a health and wellness writer covering rehabilitation, movement, exercise recovery, and evidence-informed approaches to physical well-being. His work focuses on translating complex health research into clear, accessible information that helps readers better understand recovery, mobility, and long-term physical health.


Please also review AIHCP’s Holistic Nursing Certification program and Nurse Courses see if it meets your academic and professional goals.  These programs are online and independent study and open to qualified professionals seeking a four year certification

Millions of Americans Struggle with Addiction So Here Is How Men Can Rebuild Their Lives in Recovery

Group psychotherapy for men with different problems and issuesWritten by Angela Rivera,

Getting through treatment is a major achievement. But if you’ve left a treatment program and are now thinking, “Okay, now what?”, you already understand the part that often gets far less attention: how to actually rebuild your life.

The need for actionable post-treatment support is enormous. According to the National Survey on Drug Use and Health, 44.6 million Americans had a substance use disorder in the previous year. That included 25.7 million people with alcohol use disorder and 26 million with a drug use disorder. About 7.1 million had both.

For men, it’s even harder. Men not only experience higher rates of several forms of substance use, but they are statistically more likely to end up in emergency departments or suffer fatal overdoses than women. Cultural expectations play a big role here, too. A man who has spent decades hearing that he should handle problems himself may find it especially difficult to admit that he needs help.

The good news is that recovery restores what addiction tends to take away: the ability to make deliberate choices about your time, health, relationships, work, and ultimately your future. You do not need to rebuild everything simultaneously, though. All you need is a practical place to start.

Treatment Ends But Recovery Keeps Going

The first weeks after treatment can be surprisingly uncomfortable. But understand one thing: this is normal and, in fact, to be expected.

Your schedule changes, you may sleep badly, and your appetite may be different. On top of that, you may have medical appointments, therapy, medication management, or lingering withdrawal-related symptoms to deal with. Then there are the less obvious problems: boredom, strained relationships, financial trouble, unemployment, and the sudden realization that a lot of your free time used to revolve around using.

None of these things mean that the treatment failed. They simply mean that treatment and long-term recovery solve different problems.

A person with opioid use disorder, for instance, may need ongoing medication treatment and monitoring after residential care. And someone recovering from alcohol use disorder may need continued counseling, medication, mutual-support groups, or some combination of these.

This is why your aftercare plan should come from your clinical team rather than a generic recovery checklist. Medication needs, mental health symptoms, sleep problems, and other medical concerns shouldn’t really be treated with a “wait and see” approach. They deserve professional attention.

Build a Day You Can Actually Repeat

How to make early recovery easier? Set a few daily goals you aim to hit every day.

For example, wake up at roughly the same time, eat regular meals, and take medications as prescribed. Go to work, school, treatment, or another productive activity. Exercise if you can, and attend your recovery support.

If this sounds too boring or simple, good. Boring routines have an advantage: they still work on a bad Tuesday.

Here’s another useful approach: create a “minimum day” for periods when motivation disappears. Meaning, decide in advance what you will do no matter how you feel.

That might mean getting out of bed, showering, eating breakfast, going to work, contacting your support person, and attending your scheduled meeting. This is flexible and personal, as some things may be more important to you than to others.

Get Specific About Stress

“Manage stress” may be reasonable advice, but it’s almost completely useless unless you define what stress looks like for you. So do that: what stresses you out the most?

Here are questions worth answering:

  • Do you become quick to anger?
  • Do you stop replying to texts and isolate yourself?
  • Do you start thinking about reaching out to old contacts?

Once you have your answer(s), map out your patterns using this sequence: Trigger → Warning Sign → Response

For example:

  • Argument with your partner → urge to leave and use → call your sponsor or therapist before leaving.
  • Paycheck arrives → thoughts about buying drugs → move money into essential expenses immediately.
  • Difficult day at work → isolation and irritability → eat, walk, shower, then contact someone.
  • Friday night → boredom and old drinking routines → make plans before Friday arrives.

The goal is to recognize your own early warning signs. That way, you have more room to respond before a craving becomes a crisis.

Your Living Environment Matters Greatly

What happens if you complete treatment and return to an “unsafe” environment? A place where people drink heavily, or drugs are readily available, or where everyone expects you to behave exactly as you did before. Yes, you are technically sober, but your environment is not helping you remain sober.

This is why recovery housing can make sense for many men. It’s a structured living environment that not only promotes sobriety but usually also independent growth, too, making it particularly valuable for early recovery.

If you’ve been Googling what is sober living, you probably have a good reason to consider it. There are many options, but Design for Recovery, for example, operates men’s sober living programs built around structure, peer accountability, and practical independence. Its programs include house meetings, recovery meetings, employment support, life-skills development, and a 12-Step foundation.

It’s not the same thing as detox or residential clinical treatment, though. A sober living home should not be treated as a substitute for medical or psychiatric care when those services are needed. The distinction is important when you are choosing a program because you want to know exactly what the residence provides and what it does not.

So if you’re seriously considering it, ask specific questions regarding:

  • House rules,
  • Drug and alcohol testing,
  • Meetings,
  • Medication policies,
  • Staff availability,
  • Relapse procedures,
  • Employment expectations,
  • How residents transition toward independent living.

Rebuild Your Independence in Pieces

After addiction, “get your life together” can sound like a ridiculous assignment (because it is). But here’s how you can make it work: break it down.

Work

If you already have a job, simply focus on keeping it while you stabilize your recovery. If you have been unemployed, update your résumé and apply for a manageable number of positions each week.

Keep in mind, employment is not only about income. A job can give your week structure, restore confidence, and reconnect you with a sense of responsibility.

Money

List your fixed expenses, debts, income, and immediate obligations. Pay essential bills first. But avoid trying to erase every financial mistake at once. A simple budget that you actually follow will always be better than an ambitious spreadsheet that lasts four days.

There are also recovery programs that provide financial coaching. Look for one that helps with the basics of budgeting, debt planning, credit education, and preparation for financial independence as part of its support.

Relationships

Do not demand instant forgiveness from people you hurt while using. You can apologize and make amends where appropriate. But trust usually comes from repeated behavior, not a particularly convincing conversation.

So, give people time to see that your actions have changed. You also have permission to create distance from relationships that still revolve around substance use, even if those relationships have existed for years.

Do Not Try to Replace Addiction With Isolation

Some men respond to recovery by going completely inward. They stop seeing old friends, which can be sensible. But then they stop seeing almost everyone, which creates another problem.

Peer support can provide something family members and clinicians cannot always provide: contact with people who understand the practical reality of staying sober. SAMHSA identifies peer support as a recovery resource for a reason: it can help people stay engaged, build skills, and connect with community.

You don’t need twenty new friends. Start with two or three people you can contact when things are going badly.

And make the relationship reciprocal. Listen to other people. Show up when you say you will. Help with ordinary things. Recovery communities become useful partly because people stop being isolated individuals and start becoming dependable members of a group.

Take Care of the Physical Basics

Sleep, nutrition, movement, and medical care are not side projects. They’re essentials.

Substance use often coexists with untreated medical conditions, poor nutrition, dental problems, poor sleep, and mental health concerns. That’s why medical attention is important: your primary care clinician and/or behavioral health providers can help determine what needs attention rather than leaving you to guess.

Exercise is especially important. It can help create structure and improve overall health, but you do not need to turn yourself into a fitness fanatic. A daily walk counts, and so does lifting weights a few times a week if that is something you enjoy.

A Practical First-90-Day Plan

If you need something more concrete, start here.

Weeks 1–2: Stabilize

Follow your discharge and medication plan. Keep appointments. Fix your sleep schedule as much as possible. Remove alcohol and drugs from your immediate environment. Tell at least one trusted person what support you need.

Weeks 3–6: Add responsibility

Return to work or school if you can. Establish a regular exercise routine. Attend recovery meetings or other support consistently. Start addressing debts, paperwork, transportation, and other neglected practical problems.

Weeks 7–12: Expand your life

Strengthen sober friendships. Take on more responsibility at work or home. Revisit longer-term education or career goals. Start planning what independent living will look like if you are in structured housing.

Importantly, know that the timeline is flexible. If your clinical team recommends a slower pace, follow that plan.

Recovery Has to Become a Life, Not Just an Absence

Addiction can consume an enormous amount of time and attention. Once that space opens up, you have to decide what goes there.

Work. Friends. Family. Exercise. Education. More money in your bank account. A clean apartment. A weekend you remember. Plans for next year. In short, ordinary but ultimately fulfilling things. Which is why they matter.

If you take anything from this piece, take this: you do not have to become a completely different person to recover; you just need to develop routines, relationships, and coping skills that make substance use less central to your life. For some men, that happens with outpatient care and a strong support network. For others, a structured sober living environment provides the extra accountability needed to make the transition.

Either way, the work continues after treatment. And that is not a bad thing. Treatment can help you stop the cycle, but recovery gives you the chance to decide what comes next.

References

  1. Substance Abuse and Mental Health Services Administration (SAMHSA). 2025 National Survey on Drug Use and Health (NSDUH).
  2. SAMHSA — 2025 National Survey on Drug Use and Health
  3. National Institute on Drug Abuse (NIDA). Sex and Gender Differences in Substance Use.
  4. NIDA — Sex and Gender Differences in Substance Use
  5. Design for Recovery. Sober Living Programs.
  6. Design for Recovery — Sober Living Programs
  7. Substance Abuse and Mental Health Services Administration (SAMHSA). Peer Support Workers for Those in Recovery.
  8. SAMHSA — Peer Support Workers

 Author Bio

Angela Rivera is a health writer who specializes in addiction care, telehealth, and behavioral science. With a background in patient education and evidence based communication, they focus on making complex clinical topics clear and approachable. Their work highlights practical strategies people can use to navigate recovery with confidence and support.


Please also review AIHCP’s Substance Abuse Practitioner Program and  CE courses to see if it meets your academic and professional goals.

5 Scenarios That May Point to an Occupational Health Concern  

Occupational Health written on the roadWritten by Deepika,

A patient’s symptoms often play tricks in a way that they act as footprints that don’t necessarily lead back to their origin. In other words, you may know that something has happened, but not where it all began. 

Occupation-related illnesses, although on the rise, are difficult to diagnose. A few reasons include: 

  • Similarities in clinical presentation 
  • Long latency periods between exposure and symptom onset 
  • Multifactorial etiology of chronic diseases 
  • Under-reporting of occupational conditions 

Despite the challenges, the scale of concerns makes it important to incorporate workplace cause-related health screenings. In 2024, 2.5 million non-fatal workplace injuries and illnesses were reported in the US private sector. Healthcare and social assistance recorded 3.4 cases per 100 full-time equivalent workers. 

How to tell if a patient’s workplace deserves a closer look? This article will discuss five distinct scenarios that point towards a workplace cause. 


Symptoms Improve During Time Away From Work 

In many cases, a patient’s symptoms have become such an ingrained part of their daily lives that they don’t see anything unusual. Even if the symptoms are recurring, they may not be able to connect them to their workplace. 

One important clue can be what happens when the patient is away from work. Say, coughing, wheezing, headaches, and skin irritation get better during weekends, vacations, or extended time away from work. The same return as soon as the patient resumes their work. 

The above-mentioned pattern calls for a closer look. NIOSH specifically recommends asking patients whether and how their symptoms change after a while away from work. A review of 2,050 physician charts at a large teaching hospital found that occupation was mentioned in only 28% of patient records. 

This is not surprising since it is easy to miss a relevant workplace clue during a clinical evaluation. Hence, the timing adds a worthwhile dimension to the patient’s history. As a healthcare professional, look for the following patterns: 

  • Symptoms getting worse during the work week and easing on weekends 
  • Feeling better during vacations or extended leave
  • Symptoms returning after resuming work 
  • Health issues worsening after a particular shift, task, or workday 
  • Palpable changes after moving to a different work area or performing different duties 

If there is a workplace exposure involved, it doesn’t always have to be obvious. NIOSH also recommends asking patients about new materials or activities introduced at work. Symptoms can fluctuate for many reasons, but a pattern gives it away. 

What to Do 

  • Compare the patient’s work days with their days off. 
  • Pinpoint the timing of the symptoms and their improvement. 
  • Ask directly about any workplace exposures. 


Multiple Coworkers Develop Similar Symptoms 

A workplace cause gets more difficult to ignore when multiple people develop similar symptoms. This is especially true if they belong to the same department, work area, or job role. 

The symptoms themselves do not have to be identical. Again, what matters here is the pattern. So, if several people working in the same environment begin experiencing similar issues around the same period, that’s a major sign. 

A 2025 CBS News report illustrated this pattern among Pasadena firefighters who battled the infamous Eaton fire. Captain Dave Marquez from the Pasadena Fire Department said, “For many of us, it was the worst exposure of our careers. Everybody shared similar symptoms.”

The crew had fought the fire for a brutally long 36 hours, and later submitted blood and urine samples to test for toxins. While every similar symptom may not point towards the same cause, a cluster does become good cause for questioning. Useful clues may include the following: 

  • Workers from the same area developing comparable problems 
  • Symptoms appearing after a shared workplace event or change 
  • Employees with similar duties experiencing similar complaints 
  • Unmistakable differences between affected and unaffected workers from different areas 

What to Do 

  • Ask the patient whether their coworkers share similar symptoms. 
  • Note the department, location, shift, or duties shared by the affected workers. 
  • Find out if the symptoms appeared after a specific event or change. 
  • Explore common exposure to dust, smoke, chemicals, equipment, etc. 
  • Record the patient’s account of the cluster and any workplace factors that make further evaluation necessary. 


Symptoms Start After a Workplace Change 

If a new symptom appears soon after the patient has shifted their workplace, then that may also serve as an important clue. Such a change may be obvious, such as introducing a new chemical or a piece of equipment. 

On the other hand, it may be a lot more subtle, such as moving to a different work area or changing shifts. The timing matters because it provides healthcare professionals with a specific point to investigate. Common workplace changes worth noting include: 

  • A new chemical, cleaning product, or material being introduced 
  • New machinery or equipment that produces dust, fumes, noise, or heat 
  • A change in work location, ventilation, or indoor conditions 
  • A change in schedule that alters sleep, meals, or recovery time 

Questions in this regard fall within the scope of occupational and environmental health. This branch of study examines how workplace and environmental conditions can influence health. So, those who pursue an occupational and environmental health degree focus beyond the symptoms to understanding exposures and assessing risks. 

Tulane University notes that the curriculum integrates public health principles with analytical methods in chemistry and statistics. Hence, the main focus areas are risk assessment, regulatory compliance, and exposure control. It makes sense since an understanding of the associated risk requires a more systematic assessment. 

What to Do 

  • Try finding out what exactly changed and when it occurred. 
  • Compare the timeline of the workplace change with the onset of symptoms. 
  • Ask what the patient was exposed to in the new environment. 
  • Determine whether symptoms vary with particular duties, location, or shifts. 
  • Document the suspected connection and see if further evaluation is necessary. 


A Known Workplace Hazard is Part of the Patient History 

Sometimes, the workplace connection is easier to recognize because the patient has a known exposure as part of their job. This may take the form of regular contact with chemicals, dust, fumes, biological materials, excessive heat, or radiation. 

In a 2025 field-based study, 58 construction workers in Central Florida were followed during a work shift. Then, their symptoms, hydration, and kidney function were assessed. Researchers found that 42% reported at least one heat-related illness symptom, 78% were dehydrated after the shift, and 38% showed evidence of acute kidney injury. 

It’s important to remember that a known workplace hazard is not always the cause behind a patient’s illness. However, when the patient regularly encounters a hazard that could affect their health, that exposure is a specific clinical clue worth investigating. Such a connection is especially important when: 

  • The patient regularly faces a known risk as part of their job. 
  • Symptoms appear mainly during and after the exposure. 
  • The patient has recently started working with a new substance, material, or process. 
  • The intensity or duration of exposure has increased, such as longer shifts or more time in a hot environment. 
  • Workplace protections have changed, including ventilation, hydration practices, etc. 

What to Do 

  • Ask exactly what the patient encounters at work, whether it be heat, chemicals, dust, noise, or another hazard. 
  • Find out how often or how long the conditions last. 
  • Consider whether the hazard affects the patient through breathing, skin contact, heat stress, or another route. 
  • Discuss ventilation, protective equipment, hydration, rest periods, and other controls relevant to the hazard. 
  • Think of further evaluation if the exposure and clinical presentation appear to be connected. 


The Condition is Unusual for the Patient’s Age or Circumstances 

It’s possible for a patient’s age, health history, or circumstances to not fit the condition that’s being evaluated. This is the case when a problem appears earlier than expected or has no clear, verifiable explanation. That’s when it’s time to look beyond the most common causes into the patient’s workplace environment. 

In a 2025 AP News report, this connection became a lot clearer. A Nevada dairy worker became infected with a newly identified strain of H5N1 bird flu after exposure at a cattle farm. The illness was mild, with redness in the eye and irritation as its main symptoms. 

However, the patient’s work with cattle provided an important part of their exposure history. The news report stated that at least 68 people in the US had been infected with bird flu the preceding year, with all but a small number having worked closely with cows or poultry. 

The example shows why an unusual condition or presentation may prompt a wider occupational history. As a healthcare professional, you may want to look more thoughtfully when: 

  • A condition appears unusually early for a patient’s age. 
  • The patient has few to no risk factors associated with the condition. 
  • The symptoms or diagnosis are unexpected given the patient’s health history. 
  • The patient’s occupation involves circumstances that may contribute to the condition. 

What to Do 

  • Determine which expected causes or risk factors are present or absent. 
  • Consider the patient’s occupation, daily activities, environment, and recent changes in circumstances. 
  • Ask whether symptoms began after starting a job, changing duties, or encountering a new workplace exposure. 
  • Avoid premature conclusions, treating the workplace as one possible factor. 


FAQs 

What are some signs that a health condition may be work-related? 

The most commonly observable signs include symptoms improving with time away from work, multiple coworkers being affected, and a known workplace hazard. If a condition appears to be quite unusual for a patient’s age or circumstances, that is another clue. 

What workplace factors should healthcare professionals ask patients about? 

It’s important to ask about chemicals, dust, fumes, heat, noise, biological materials, ventilation, and recent workplace changes. Also, consider asking whether the patient knows anybody from their workplace with similar issues. 

What should a healthcare professional do if a workplace cause is suspected? 

The first thing to do is to establish the timeline and compare symptoms across work and non-work periods. Then, document the relevant findings and consider appropriate health evaluation. A suspected connection should guide further assessment rather than being treated as proof of causation. 


Workplace Clues at a Glance 

What You Notice  What to Look For 
Symptoms improve away from work.  Better on weekends or leave 
Symptoms follow a workplace change.  New task, material, equipment, or location 
Coworkers have similar symptoms.  Shared duties, area, or exposure 
A known workplace hazard is present.  Heat, dust, fumes, chemicals, or noise 
The condition seems unusual.  Early onset or unexplained presentation 
Key questions to ask  Timing, tasks, exposures, and coworkers 
Clinical takeaway  Investigate patterns without assuming causation. 

As we discussed, the context surrounding the symptoms tells the whole patient story. So, when symptoms occur, whether coworkers are affected, and what conditions the patient encounters are all equally important. 

As per a 2026 study of 734 healthcare workers, workload, night shifts, and noise were all associated with occupational fatigue. Again, we see how several workplace factors can influence health at the same time. 

Next time a patient’s condition does not fully explain itself, look into their workplace conditions as well. A few thoughtful questions may reveal connections that are otherwise overlooked. 

Author Bio

Deepika has over six years of experience as a writer and editor. Passionate about words and learning, she takes an interest in a variety of niches. Her knack for turning complex ideas into relatable narratives allows her to resonate with the reader. When her pen falls silent, you can find her engrossed in a novel or getting her hands messy with fine arts. Through these, Deepika is committed to keeping her curiosity and creativity alive. 


References:

  1. Economics News Release. Employer-Reported Workplace Injuries and Illnesses (Annual) News Release. January 2026. US Bureau of Labor Statistics. 

https://www.bls.gov/news.release/osh.htm

  1. Saif Nadia, Socias-Morales Christina, et al. Primary Care and the Working Patient – Occupational Health Principles in Practice. October 2024. National Institute for Occupational Safety and Health. CDC. 

https://www.cdc.gov/niosh/bulletin/2024/primary-care-oh.html

  1. Tan Lanhui, Zhang Ruyi, et al. Multiple exposure sources and occupational fatigue profiles among healthcare workers: a cross-sectional latent profile analysis. 2026. Frontiers. 

https://www.frontiersin.org/journals/public-health/articles/10.3389/fpubh.2026.1811642/full

  1. Chicas C Roxana, et al. Acute Kidney Injury Among Florida Construction Workers: A Pilot Study. March 2025. PubMed. 

https://pubmed.ncbi.nlm.nih.gov/39706579/


Please also review AIHCP’s Health Care Certification program and CE courses see if it meets your academic and professional goals.  These programs are online and independent study and open to qualified professionals seeking a four year certification





